BOTOX Cosmetic Day: What a Deal Changes, and What It Never Will

Black and white editorial close-up of a woman's face in three-quarter profile, eyes closed, a gloved hand holding a fine syringe just above her brow, dramatic side light. Illustrative generated image, not a real person and not a patient. Commentary by Frank Agullo, MD, FACS, Dr. WorldWide.

Allergan’s BOTOX Cosmetic Day is next Wednesday, November 18. From 12 pm Eastern, Allē members can buy a $50 BOTOX Cosmetic gift card online and get a second one free, one purchase per member, while they last. The cards do not expire. It is the company’s biggest offer of the year, and in my practice it is the busiest injectables week on the calendar.

I like the day. I get toxin myself, and I have said so in print.

“It really is a maintenance therapy. I myself get botulinum toxin in the forehead, crow’s feet, and glabella lines every three to four months, just to maintain the wrinkle free appearance with a dose that still lets me express my face without looking abnormal. I believe the skin quality in these areas is also maintained with the use of botulinum toxin.”

So here is what the deal changes. It changes the price of a treatment I already think is worth having, for people who already know they want it. That is all it changes, and the rest of this post is about the things it does not.

It does not change the dose.

“Patients also need to understand that a lot of things matter in regard to how long the Botox treatment will last. Dose, dilution, injection placement, and product choice matter more than whether you are active or inactive. These are all customized depending on each patient’s consultation. For example, patients with very strong frontalis muscles, glabellar muscles, or masseters will require a higher dose than others.”

A first-timer who asks how many units two gift cards buy is asking the wrong question. The exam sets the units. The cards come off the bill afterward.

It does not change what is in the vial, or who is holding the syringe. Deal weeks bring discount offers from places that are not Allergan, and I wrote down last month exactly how my practice keeps that out of the room.

“We buy directly from the manufacturers, Galderma, Allergan, and Evolus. The toxin is shipped to us directly from them in temperature controlled containers. The vials are stored in a medical temperature controlled refrigerator that is monitored 24 hours a day for temperature variations.”

“We do not use a middle man or discount pharmacy to order our toxins. Botulinum toxin are reconstituted and administered by registered aesthetic nurses, nurse practitioners supervised by Dr. Agullo. Dr. Agullo also administers the treatments. Patients can see the vial at any time.”

“The danger with counterfeit products is that we only find out because they go to the ED because of severe life threatening complications. Some counterfeit products result in no result at all because they do not contain the botulinum toxin.”

And it does not change the day-after rules.

“I do ask patients not to exercise for twenty-four hours after a botulinum toxin injection, but this is not because it is going to wear off sooner. It is because I want the solution to stay exactly where I injected it, and strenuous exercise immediately after an injection could increase the risk of the product migrating, complications, and swelling.”

One more thing a deal day cannot do: it cannot turn a surgical problem into an injectable one. Toxin relaxes a muscle. It does not lift a brow that has fallen or remove skin that is resting on the lashes. If you have been adding units every visit and getting less, that is the conversation to have, and it is on the Agullo Plastic Surgery version of this post.

The deal mechanics, the table of what the cards cover and do not, and how the front desk at Southwest Plastic Surgery applies them are in the full post. My read on the two-week toxin that is not here yet is in Boey.

Ready to Talk?

I am Frank Agullo, MD, FACS, double board-certified, Mayo Clinic fellowship trained, Clinical Associate Professor of Plastic Surgery at Texas Tech, Castle Connolly Top Doctor 2014 through 2026. Call (915) 590-7900, text 1-866-814-0038, or book at swplasticsurgery.com/med-spa. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Reuters Says Men Are Finishing Their Weight Loss at Cosmetic Clinics. Here Is What I Told the Reporter.

Black and white editorial portrait of a lean man in his forties in a dark shirt, three-quarter profile against a plain studio backdrop, hard light tracing the hollow of his temple and the line of his jaw. Illustrative generated image, not a real person and not a patient. Commentary by Frank Agullo, MD, FACS, Dr. WorldWide.

Reuters ran it on August 28 under the headline “Beyond the Scale.” Men, the story said, are taking their GLP-1 weight loss to cosmetic clinics to finish the job. The American Society of Plastic Surgeons counted 1.7 million cosmetic procedures on men in 2024, up 2.7 percent, with eyelid surgery, liposuction and tummy tucks at the top of the list, and its president said nearly 70 percent of the men who had surgery in the first quarter of 2026 had used one of these drugs.

I was one of the sources the reporter asked in June. I dictated an answer and sent it. It did not run. That is fine; a piece has room for four voices, not forty. But the answer is still the most honest thing I have on the subject, so here it is, in the words I sent.

The first thing I told her is that the “side effect” is not a side effect.

“The side effects of GLP-1 weight loss drugs showing up in cosmetic settings is mostly the fact that, ironically, patients are seeking treatment. Of course, with weight loss, we lose the fat volume in areas where we don’t want to. The loss of fat in the face ages us dramatically.”

And that the men who look oldest afterward are the ones who only did half the program.

“We especially see it in patients who are only doing the diet portion of the GLP-1s. That is, the GLP-1s make them eat less and have less appetite. They lose weight rapidly but are not doing an exercise regimen to build up muscle, so they lose muscle mass as well. This rapid weight loss gives way to what we are now calling ‘Ozempic face,’ which is the rapid aging.”

A face ages on two tracks, and a GLP-1 patient runs both at once.

“As we age, there are two factors: one is skin laxity, and the other is volume loss. So in the GLP-1 patient, what we are seeing is skin laxity, because the skin was stretched out previously, along with rapid volume loss. It really results in rapid aging.”

Here is the inventory, which is longer than most stories admit.

“We are seeing the deep nasolabial lines, the marionette lines, and the hollowness under the eyes. There is temporal wasting and sagging of the skin underneath the chin, platysmal banding, and loose skin. We are seeing skin sagging and breast sagging, with loss of volume in the upper poles, as well as buttock sagging and buttock ptosis, all at the same time because of the rapid weight loss.”

Men come in earlier than they used to, and they come in for the face first.

“I am seeing a surge in men seeking cosmetic procedures in the early stages of their weight loss. They want to hide the facial aging, so a lot of times we are injecting fillers like Sculptra, or fillers underneath the eyes and the temples, in the cheek area, and in the nasolabial lines. They are starting to use Botox as well to raise the brows.”

Then the body, and then the point where the non-surgical tools run out.

“As the weight loss continues, we are seeing men having other procedures, like gynecomastia procedures to fix the chest, and tummy tucks. We are also seeing them undergo liposuction with skin tightening devices such as Renuvion J-Plasma, fat transferred to the buttock, fat transfers to the face, and even buttock lifts and tummy tucks.”

“I am increasingly seeing more patients for facial work as they continue to age and the fillers and skin tightening devices stop working. So we are seeing increased demand for neck lifts, face lifts, brow lifts, and upper and lower eyelid surgeries.”

The story’s framing was clinics adapting to a new market. I pushed back on that.

“I don’t think it’s really a question of how clinics and providers are adapting. We have always had these tools, and we had been using them on weight loss patients after bariatric procedures. But we had not seen weight loss this rapid before, which of course has increased our volumes.”

And the last thing I told her is the thing I would have led with.

“In the end, these patients undergoing GLP-1 therapies are becoming healthier. As they become healthier, they also want to look healthier and better, so they are seeking out cosmetic procedures. Sometimes the cosmetic procedures cannot keep up with the aging caused by the dramatic weight loss, and surgical procedures need to be performed. Overall, the patient becomes healthier as their medical problems improve or disappear.”

“You can see the evolution of these patients, because we do treat patients with GLP-1s in our clinic. You see how even the patient starts dressing differently, how they carry themselves when they come in, and how their whole outlook on life and self-esteem improve.”

That is the whole answer. The order I treat it in, stage by stage with a table, is in the full post on Agullo Plastic Surgery. The med spa half, where most of these men start, is on Southwest Plastic Surgery. Three of the consults behind it are nearly verbatim here, and the numbers from my own schedule are in one in three consults.

Ready to Talk?

I am Frank Agullo, MD, FACS, double board-certified, Mayo Clinic fellowship trained, Clinical Associate Professor of Plastic Surgery at Texas Tech, Castle Connolly Top Doctor 2014 through 2026. Call (915) 590-7900, text 1-866-814-0038, or book at agulloplasticsurgery.com/appointments. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Twenty New Faces: Why Every After Photo I Just Posted Is a Year Old

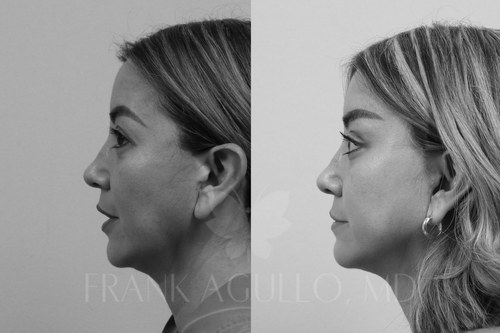
Black and white before-and-after photograph of a facelift patient from the Agullo Plastic Surgery gallery. Actual patient, published with consent.

We added more than 20 new cases. All of the photos are more than one year out for the rhinoplasty and facelifts. We added them for patients to see the latest results using the latest techniques.

A year is the number that matters in that paragraph. A nose at three months is still swollen at the tip; a face at six weeks has healing in it. The photo nobody is in a hurry to take is the result, and it is the only kind I post.

What is in the batch, in the words I gave the office:

I would like everybody to know that there are new before-and-after images for facelift and rhinoplasty in the gallery. The before-and-afters are of open rhinoplasties, primary lower facelifts, neck lifts, and full facelifts. Some of the cases are with the total endoscopic deep plane total facelift, also known as the ponytail lift. Most of the cases are combined with other procedures, including Morpheus8, fat transfer to the face, upper and lower blepharoplasty, buccal fat pad removal, and even a lip lift.

On the noses:

As is usual in my rhinoplasties, they will see very harmonious results that go with the patient’s face. It does not change the patient’s face per se but usually rebalances it and improves the overall aesthetics. They will also notice that all the noses are different and they’re not cookie-cutter templates. Each procedure is individualized accordingly for each patient and their needs. Of course we perform Vectra or Crystalux 3D imaging to help the patient visualize the results before surgery and also to improve communication with me so that we are certain that we’re both on the same page.

They are in the rhinoplasty gallery and the facelift gallery on my surgical site, with a longer note on what each batch shows in the gallery post. More photos are coming over the next few weeks. The practice’s note is on Southwest Plastic Surgery.

I am a double board-certified plastic surgeon, a Mayo Clinic fellowship alum, and a Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. Every photo is my own patient, published with consent. Ask any surgeon you are considering when their after photos were taken.

Call the office at (915) 590-7900, text us at 1-866-814-0038, or book a consultation at agulloplasticsurgery.com/appointments.

#StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Who Is Holding the Punch? World Hair Transplant Repair Day and the Clinics That Keep It Busy

Black and white editorial photograph of a man in a dark shirt seen in close profile against a plain studio backdrop, hard side light tracing the edge of his hairline. Illustrative generated image, not a real person, not a patient photograph and not a result. Commentary by Frank Agullo, MD, FACS.

A hair transplant is the only operation I know of where the patient routinely never meets the surgeon. That is not a figure of speech. In the clinics the International Society of Hair Restoration Surgery calls black market, there is no surgeon to meet.

Today is the sixth World Hair Transplant Repair Day. About a hundred ISHRS physicians around the world will do a corrective transplant for free for someone who got hurt that way. I am a member, and I read the society’s numbers this year with the feeling you get when a problem you thought was somewhere else turns out to be down the street. In the 2025 practice census, 59 percent of surveyed members said black-market clinics operate in their city. In 2021 it was 51 percent. One in ten repair cases those members did last year followed a black-market transplant, up from six in a hundred three years earlier.

The Thing That Gets Sold

What gets sold is a graft count and a price. Five thousand grafts, a package, a hotel, a flight. What does not get sold, because it cannot be, is a surgeon’s judgment about your scalp. I told Men’s Fitness last month that a price that is far too cheap often means a technician is operating, and I will stand by that line on any day of the year.

Here is what the judgment sounds like when it exists. This is me, in my own exam room, to a man who wears a high fade:

“So when people wear the hair short on the back, that’s where we get the hair from. So those are the follicles that we use to fill in the front. So one way to take them from the back is doing the FUE, which is the one by one, the neograft. We take them one by one, it heals in, and you don’t see any scars. The other one is doing a strip where I actually cut like a sliver of hair follicles or scalp, but it does leave a scar. So if you wear your hair short, you would see that long scar.”

And this is me saying no to a number, which is the sentence a package deal never contains:

“With the FUE, we can do maximum twenty-five hundred, sometimes twenty-eight hundred follicles.”

“Three thousand’s the limit, because more than that we really can’t get out of one strip.”

The donor area is a bank account. A surgeon tells you the balance. A clinic tells you what you want to hear and overdraws it, and the overdraft is permanent, because the hair that was pulled from the back of your head does not grow back there.

Technicians Are Not the Villain

I want to be fair about this, because the word “technician” gets thrown around as if it settled the argument. Trained technicians handle grafts in every serious hair practice, including mine:

“We do a minimum of a thousand grafts at a time, just because I bring the techs in from out of town, but that will fill in pretty nice.”

The difference is who they work for. In my practice they work under a surgeon who examined you, designed the hairline, chose the method, and will be the one looking at you at six months and a year. The ISHRS says it is a lifetime relationship, not a one-day transaction, and that is exactly the difference. The clinic’s relationship with you ends when the deposit clears.

What I See When It Went Wrong

The repairs come in a handful of shapes. A hairline drawn too low and too straight on a young man, which looks fine at 25 and strange at 40. Grafts placed in rows, so the front edge reads as a doll’s head. A donor area harvested until it is patchy, which is the one with the fewest options. A strip scar that was never warned about and sits above a short haircut.

Some of that I can fix. Grafts come out and go back in higher, single hairs go on the front edge, density gets added behind, a widened scar gets hair grafted into it. Two years after a strip transplant one of my own patients wanted more density, and the answer was simple:

“It looks good, but you can see that there’s a little bit of distance between them, because that’s the way we have to do it. So now we can go in between.”

Some of it I cannot fix, and the honest consult is the one that says so. A transplant moves hair; it does not make new hair. When the donor supply is spent, the plan is medication, a hair system, or scalp micropigmentation, and anyone who promises otherwise is selling the same thing that caused the problem.

What to Ask Before Anyone Touches Your Scalp

Who examined me, and is that the person who will operate? Who is designing the hairline? How many grafts does my donor area allow, not how many will you sell me? Whose license is on the consent, and can I check it with the medical board? Who sees me at a year?

A practice answers all five without flinching. The full checklist, the ISHRS definition, and what each kind of repair involves are on my surgical site. The practice’s version, with the PRP and exosome side of a repair, is on Southwest Plastic Surgery. The consult that decides strip or FUE is in my FUE read.

I am a double board-certified plastic surgeon, a Mayo Clinic fellowship alum, a Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center, and a member of the ISHRS. I also have a hair transplant of my own, done by strip. I know what the scar looks like, and I know what it is to wait a year to see whether it worked. I would not let someone I had never met do it to me.

Call the office at (915) 590-7900, text us at 1-866-814-0038, or book a consultation at agulloplasticsurgery.com/appointments.

#StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

The Weight You Keep Is the BBL You Keep: What I Tell Patients on RealSelf

Black and white photograph of a woman in a fitted dark dress standing in profile against a plain studio backdrop, one hand on her hip, hard side light on the line of her hips. Illustrative generated image, not a real person, not a patient photograph and not a result. Commentary by Frank Agullo, MD, FACS.

“Do I need to gain weight for a BBL?”

That is probably the question I get most on RealSelf, and I have been getting it since 2017. The only difference is that back then it came with a photo and a height and weight. Now it comes with a GLP-1 prescription and a plan to lose the weight afterward.

The long answer starts with the fact that grafted fat is living tissue. It grows and shrinks like any other fat in your body. Weight gain or loss does the same thing to the fat I moved to your buttock as it does to the flanks I took it from. So every candidacy question is a weight question, and the key to a result that lasts is staying close to the weight you had on the day of surgery.

Five of those questions, paraphrased and stripped of identifiers, with my answers lightly edited for publication.

“Do I need to gain weight for a BBL?”

Answered on RealSelf, Jun 2017.

From your photos it seems that you would be a good candidate for a Brazilian butt lift. I would recommend taking fat from all possible areas including abdomen, lower back, upper back, and possibly medial thighs. I would be able to obtain more dramatic results with a 10 to 15 pound weight gain, but you would have to maintain the new weight after surgery. If you are looking for a more dramatic result, you might want to consider the use of buttock implants as well.

“Should I lose weight first? I am 150 now and used to be 115 to 120.”

Answered on RealSelf, Nov 2023.

When it comes to procedures like a BBL with lipo 360, weight plays a big role in deciding the right time to have surgery. At 150 pounds your BMI is 26.5, which technically puts you in the overweight category, but just barely.

If you are unsure what weight you should be at before the procedure, think about the weight you are most comfortable at and most likely to maintain after surgery. If 150 pounds is a weight you are happy with and can keep after your BBL and lipo 360, then this is a good weight to have the surgery at (knowing that you will probably lose about 5 pounds from the fat removed). On the other hand, if you feel you will likely return to your earlier weight after the procedure, it is best to wait until you are closer to that weight. Big weight changes after a BBL or lipo 360 can alter your results, so having the procedure close to the weight you will keep gives you the most stable, longest-lasting result.

“Does going over the muscle limit the fat, and how much survives?”

Answered on RealSelf, Nov 2023.

Where is the best place to put the fat in a Brazilian butt lift, into the muscle or over it? There has been real concern about putting fat into the muscle because of fat embolism (fat getting into blood vessels and traveling to the lungs), so the guidelines now recommend placing fat over the muscle. Some surgeons think the result may be better with fat placed into the muscle (more lift, a better scaffold for the graft), but for safety I recommend grafting over the muscle.

Will you still get a good result without fat in the muscle? Yes. There is a finite amount of space over the muscle, but a large Brazilian butt lift can still be achieved in experienced hands. Depending on the study, fat survival over the muscle runs 50 to 70 percent, and the rest is reabsorbed by the body. So depending on the amount and quality of fat available, the technique used and the post-operative care, your goal of wider hips and a larger buttock can be reached.

Three years on, I would put it more bluntly. I graft above the muscle only, with an ultrasound probe on the skin so I can see the cannula the whole time. There is no version of “into the muscle” that I do. If a surgeon tells you more fat survives in the muscle, ask what else travels there.

“Is 500 cc per side enough?”

Answered on RealSelf, Oct 2018.

The amount of fat to be injected into the buttocks and hips is determined by your current body composition and your objectives. With 500 mL, you will definitely improve the projection and contour. Most of my patients have 1,000 mL or more during their BBL. Keep in mind 30 percent of the volume will go away during the first four to six weeks.

“Is it okay to lose 15 to 20 pounds after a BBL?”

Answered on RealSelf, Jun 2017.

It is okay to lose weight after a BBL. Keep in mind that after a Brazilian butt lift your new shape is locked in. With weight loss your buttock is likely to get smaller but would maintain the same curves.

The 2026 version of that question came with a weight loss injection attached:

Your grafted fat in the buttocks is still living fat, so if you shed pounds, your buttock fat will shrink right along with it. Ten pounds is actually a minor amount, and a gradual, slow rate of loss is more forgiving to your BBL’s overall aesthetic compared to rapid or crash weight loss. You will probably notice a slight decrease in your buttock’s prominence.

What I Would Say to All of Them

I am in the business of building shape. You are in the business of keeping size.

If you think you are too thin for a BBL, chances are I can still snatch the waist, fill the hip dips and round out a flat buttock, and I can do it safely as long as your BMI sits under 35. What I cannot do is make the graft ignore your metabolism. Gain 20 pounds for the surgery and lose them after, and the extra fat I harvested deflates with you. Take a GLP-1 a year later and lose 30, and the curves stay while the volume follows the scale, which is the whole subject of my 360 deflation post.

The full set of six questions, with the BMI cutoffs and the thin-patient graft numbers, is on my surgical site. The practice’s version is on Southwest Plastic Surgery. Where my 35 comes from is in the BMI post, and the science of why half the fat stays and half does not is in BBL fat survival.

I am a double board-certified plastic surgeon, a Mayo Clinic fellowship alum, a Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center, and a founding vice president and president of the World Association of Gluteal Surgeons. The weight question is the one I ask first because it is the one that decides what you keep.

Call the office at (915) 590-7900, text us at 1-866-814-0038, or book a consultation at agulloplasticsurgery.com/appointments. My answers are on RealSelf.

#StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Kathy Griffin’s $218,000 Facelift: What a Six-Figure Price Tracks, and What It Does Not

Kathy Griffin smiling on the carpet at the 35th Annual EMA Awards Gala in Studio City, California, October 11, 2025, two months after the facelift she describes. Commentary by Frank Agullo, MD, FACS.

Two hundred and eighteen thousand dollars. Kathy Griffin said the number out loud on a podcast last fall, and E! put it at the top of its celebrity procedures by the numbers roundup this month. Her third facelift, done in August of last year. “It was not cheap,” she said. Then came the part that made me put my coffee down: she called it a bargain, because, by her account, six or seven surgeons in Beverly Hills charge up to a million.

Kathy Griffin smiling on the carpet at the 35th Annual EMA Awards Gala in Studio City, California, October 11, 2025, two months after the facelift she describes. Commentary by Frank Agullo, MD, FACS.
Kathy Griffin at the 35th Annual EMA Awards Gala, Studio City, California, October 11, 2025. Photo: MLM IMAGES Los Angeles/Shutterstock, editorial use.

I’m not her doctor and I have not examined her. I am not going to guess at who her surgeon is, and I am not going to rank her face on some scale. What I can do is read a bill. I write facelift quotes every week, so I have a pretty good idea of what goes into a number like that.

What a Facelift Bill Is Made Of

Let me start with mine, since it is the one I can itemize line by line.

“The fee covers the surgeon’s fee, the anesthesia, the accredited surgical facility, your medical tests, your garments, and your recovery products. Prescription medications from the pharmacy are the one thing you pay separately.”

Then the hours. Mine are not short, on purpose.

“I allow sufficient operating room time to work in a paced fashion, for safety. Low-cost surgeries get compressed to cut anesthesia and operating room fees.”

Then the add-ons, where quotes really diverge.

“With most facelift procedures we also do fat grafting. We usually recommend Morpheus8 with Iriescence PDGF, or the Sciton MicroLaserPeel with Profractional, depending on your skin type. We can also use exosomes or nanofat. We recommend ELIXIR MD, which is LED light therapy, for almost double the speed of recovery. And a lot of patients will require an upper blepharoplasty, a lower blepharoplasty, a lip lift, or an earlobe reduction. Those all do increase the cost.”

Surgeon, hours, anesthesia, facility, city, and whatever else was done under the same anesthetic. The surgeon’s name is the biggest line. The zip code is the second.

What the Price Tracks, and What It Does Not

The number tracks The number does not track
Surgeon demand and experience Whether the result looks natural
Hours in the operating room Whether the midface was actually moved
Anesthesia, facility, nursing How long the result holds
The city (Beverly Hills is its own market) The scar quality
Everything combined in the same anesthetic Whether the patient is recognizable afterward

“Cost varies with the doctor’s experience. Surgeons in high demand consistently deliver good results in a safe environment with top-quality products, and that increases cost.”

Demand sets the price. A price is a signal, not a guarantee, and past a point the signal flattens.

Does $218,000 Buy a Better Face?

No. It buys a surgeon’s time in an expensive city, and probably the full menu in one sitting. The result comes from the plane, the release, and the restraint of the hands.

“I think the deep plane lift and the endoscopic deep plane lift are great procedures, which create very natural and long-lasting results, and we’re seeing patients completely avoid the noninvasive procedures and go straight to the surgical procedures early on.”

“I think patients are becoming a lot more willing to undergo facial procedures, including facelifts, because the results now are actually natural and do not change their overall appearance. So they still have a self identity after these procedures and they’re recognizable; they’re just looking ten to fifteen years younger.”

Recognizable. That is the test, and it is free. More in the facelift you can’t see and month eighteen. No prices in either.

A Third Facelift in 27 Years

Griffin’s first was in 1998, at 38. The third at 64. That is not vanity, that is biology.

“We know that with aging, fat will decrease in the face regardless, so it is a procedure that we probably have to repeat in the future.”

“A facelift will change the position of the tissues,” not the amount of them. The skin keeps aging. Which is why I tell people, “So we have to have realistic expectations, especially when you’re a lot older.” And, from a roundtable in Boston this spring, “if you operate on somebody that’s 30 or 40, it’s not the same as somebody that’s 70 or 80.”

A third lift is also harder: old planes, old scar. Part of what a veteran charges for.

Too Good to Be True Cuts Both Ways

Expensive does not mean safe. Cheap is the one I worry about.

“I always feel like when things are too good to be true, they usually are. If a price seems far below what everyone else is charging, you have to ask what’s being cut, the surgeon’s experience, the accreditation of the facility, the type of anesthesia, or the follow-up care.”

“Our patients get direct nurse access 24 hours a day, and all surgeries are done in an accredited surgical center.”

Ask a six-figure quote the same four questions. What is included, how many hours, who gives the anesthesia, who answers at 2 a.m.

My Numbers, for the Record

My tiers are on the fees page and itemized in what a facelift costs. A full deep plane facelift in El Paso is a fraction of this number. Not less surgery. Less zip code.

Why Choose Dr. Agullo

Dr. Agullo is certified by the American Board of Plastic Surgery and the American Board of Surgery, completed his plastic surgery fellowship at the Mayo Clinic, and serves as Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. He trained in the endoscopic deep plane lift at the Ponytail Academy in Pittsburgh (intermediate) and Santa Monica (advanced). He has been a Castle Connolly Top Doctor for thirteen consecutive years, 2014 through 2026. More than eighty percent of his patients travel to El Paso from across the country.

Ready to Talk?

Bring your quote from anywhere. I will tell you what each line pays for, what I would do differently, and what my number would be.

Call (915) 590-7900, text 1-866-814-0038, or book online at agulloplasticsurgery.com. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

“How Bad Is the Scar Going to Be?” One Week of Answers, Nearly Verbatim

Black and white editorial photograph for scars after plastic surgery commentary by Dr. Frank Agullo, MD, FACS.

I draw the incision on the skin with my finger, and the next question is almost always the same one. This week it came from a patient with an old scar over a joint that healed thick, from a patient who is pale and expects the worst, from a patient with two areola scars that stretched wide, and from a patient finishing a course of Accutane. I am publishing the exchanges nearly as they happened, identifiers removed.

The patient with the ugly scar

Her: The scarring. I’ve had surgeries before, but this one kind of healed really ugly.

Me: “That’s typical of any scars over the joints. They’re always gonna be worse. So the ones that we can control, like in the breast and in the abdomen, they usually do much better. We will be doing taping and then silicone taping, and then we’re gonna be using a scar cream. So we’ll be on top of it to try to get the best scar we possibly can. And the good thing is that the way I place all these scars, they’re really gonna be hidden by underwear or a bathing suit, or the bra or a bikini top. So all of them are gonna be easy to hide.”

Her: And you said it would have to be from here to here?

Me: “Yeah, it’s where your fold ends, but it is in the underwear or bikini line, so it’s easy to hide. And going that far allows me to remove the excess that you have on the side, because if we only do the front, then you’d keep the sides, like wings, or we call them dog ears.”

The pale patient

Her: I feel like my stomach’s okay. But I’m pale, so I scar pretty intensely. I have concerns about scars.

Me: “You should actually scar very well. Because the lighter you are, the better the scars are. There are areas where everybody scars bad. So elbows, knees, any joint, or in the chest area, everybody’s going to get a bad scar. But in other places, usually the lighter the skin, the easier the scar is.”

She was also asking about her inner thighs, and that is the one incision I warn everybody about.

Me: “Whenever we do a medial thigh lift, I can tell you almost a hundred percent of the time something will open up a little bit, so it does take some changing the gauze until it heals, so that delays the recovery a little bit. Usually it heals perfectly well. We don’t have to do any scar revision or anything, but there’s so much tension in that area that it always opens up a little.”

The patient with a C-section scar

Her: You said it was gonna be an extended? My C-section scar is from here to here.

Me: “Yeah, we’re gonna remove that, and then it’s gonna go, in your case, to about here.”

Her: Does it go like a smile type of position?

Me: “It follows your crease right now. Your underwear, you’re not wearing it that high, so it would probably not be a good idea to put it that high. It’s more in the panty line.”

The patient with stretched areolas

Me: “So I think that we have a good chance if I just stick to really not trying to make them much smaller, but just the scar. It has to be full thickness, but I think we can get it, because it’s still soft, so it’s not very tight. So we’ll just be redoing both areolas, and hopefully try to avoid having to do the vertical. One of the things we’ve started using is microneedling and PDGF, which is a platelet-derived growth factor. I can inject that during the surgery, and then you can actually take some home and apply it in the scar, and it does seem to really make the healing a lot faster.”

Her: Would it have to be under general?

Me: “This can be under IV. But not local. It’s a very sensitive area. And it would take like an hour, and then you go home the same day. You can go back to work probably in two, three days, and then exercise we would wait at least two to three weeks, four weeks to be sure.”

The patient who wanted an old scar gone

Her: There’s some scars on the side of my eyes. Is that something that can be removed?

Me: “At the time we do the blepharoplasty we will revise those. We can’t get rid of scars, but we can make them look better. I have to cut them out and close them, and then do the wound care and everything so that it heals better than it did the first time.”

She also had a scar above the brow from an old brow lift.

Me: “The absolute best way to hide that scar is to actually take some hairs from the back and transplant them in front of the scar so it hides it. It’s hair that we move from the back into the front and it’s gonna grow really well. The other option is for me to try to redo your scar, but it may heal the same again. So if we can actually hide it, it’s even better.”

The patient worried about a scar on her nose

Her: I don’t know if I’ll do anything on the side, because I don’t think that I want that scar.

Me: “That scar heals pretty well. The most important thing is in the beginning keeping it very clean, because if a scab builds up, then you get the little indent. But afterwards, we can do microneedling, and it’s going to be right on that ridge, and you have the advantage that you use makeup to conceal it. So it’s really not that bad. In guys, it’s something I tell them to really think about, because you have no way of hiding it.”

Her mother: She tends to scar strong sometimes.

Me: “There are areas in the body where everybody scars bad. One is the chest, and then any joint, like elbows, knees. In the face, everybody usually scars really, really well. I’ve actually never seen a keloid on the nose.”

The patient on Accutane

Her: And with Accutane? They told me I should be done this month.

Me: “The only worry we have with Accutane, it’s really when we do work on the face, because they can scar. This is such a small incision that really we don’t worry about it. Accutane only really affects the skin, and it’s right on the fold, so it’s really not an absolute contraindication. Worst case, if your scar doesn’t come out beautiful, once you’re off Accutane we can revise it and make it look better. But we’ve done patients before, and they do perfectly fine. You just have to do a lot of moisturizer, so that when we put in the implant, I would even start today, so that we avoid stretch marks.”

What all of them heard, in some form

Scars depend on how much skin you have. Skin type, location and tension decide most of the result before the first stitch goes in. My part is to put the line in a crease or under clothing, keep the tension off it, and stay on top of it with tape, silicone and cream. If a scar still disappoints us, I cut it out and close it again, and sometimes the better answer is to hide it under hair.

I am a double board-certified plastic surgeon, a Mayo Clinic fellowship alum, and I teach plastic surgery as a Clinical Associate Professor at Texas Tech University Health Sciences Center.

Call the office at (915) 590-7900, text us at 1-866-814-0038, or book a consultation at drworldwide.com.

#StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Bobbi Althoff Wants a Little Sag: A Surgeon Reads the Implants-After-Nursing Plan

A mother holding her baby in a bright kitchen. Illustrative image, not a patient. Commentary on implants after breastfeeding by Frank Agullo, MD, FACS.

Bobbi Althoff, 29, says she is getting implants in January. Six years of nursing two daughters, with overlap. She thought about a lift, passed, because more kids are likely. And she wants “a little bit of a sag.” People had it October 29, via Yahoo; The Blast added a hair transplant the next day.

View this post by Bobbi Althoff on Instagram

Bobbi Althoff on Instagram (@bobbi), September 29, 2026. Embedded from her public account; the photos belong to their owners.

No surgeon named. I have not examined her. So, no diagnosis. Just the plan, which I hear every week.

A Little Sag, in My Words

More of my patients ask for less:

“I have an increased number of patients looking for slight changes using implants under three hundred CCs, and even using the Motiva Preserve procedure for a much faster recovery.”

What they mean:

“The patient that comes in looking for the ballerina look is usually asking for a subtle augmentation with an upper pole slope, without too much upper pole fullness, and an overall natural, not done look. This is usually a look that is achievable with a patient that is not very large breasted to start with.”

The implant that does it:

“It’s ergonomic, which means the implant actually moves with you. So this implant is a gummy bear, but it’s round when you lay down, and when you stand up, it kind of turns into a teardrop. So it’s more natural. It’s pretty soft.”

And where it goes:

“When implants are under the muscle, the muscle is always pushing them to the sides, so eventually they move to the sides, and whenever you lift or contract the muscle, it looks less natural.”

“Those older patients I showed you were under the muscle because Motiva wasn’t available yet. Before Motiva, we put everything under the muscle.”

“When you see them move and contract during exercise, that means they’re under the muscle. Over the muscle, you don’t see that.”

Skipping the Lift

The rule I use:

“If the nipple areola complex is below the inframammary fold, then a full lift, anchor type incision, will be necessary. If the nipple areola complex is at or slightly above the inframammary fold, I will often recommend a circumareolar lift or donut lift.”

“If the lift is not performed during the augmentation and there is considerable sagging, then the implants will appear to be higher up, even though they are in the right place, and the nipple areola and breast tissue will hang over it.”

A mom of three, nursed for years, measured at 23:

“The nipples are a little bit low. With the implant, it does lift up a little bit, without having to do any lift per se.”

“You can see it gives you the volume where you’ve lost it, which is the upper part. Gives you more projection. It lifts it up a little bit. From the top, you get a nice cleavage, but it’s still, we call it ballerina breast, because it’s not obvious that there’s an implant there.”

And when a lift is done anyway:

“As you can see, when we do the doughnut lift, it still has kind of a natural slope to it. But it’s considerably perkier than before.”

“A breast lift will always give a perkier look, more upper fullness, and cleavage, but it’s going to have usually a natural slope on top.”

Sag, either way. Just planned.

More Kids First

Her reasoning holds. My version:

“Patient who wants augmentation before she is done having kids: go ahead. There are still going to be changes in the breast with or without implants. Surgery may be necessary after pregnancy even without implants, for a more cosmetic and aesthetic look.”

On nursing, I promise nothing:

“Either way, there is a risk that you will not be able to breastfeed, but that risk also exists even if we do nothing, because we do not know.”

With Preserve:

“These implants are going over the muscle. I’m not doing any cutting. So the pocket is made just by moving everything to the sides. That’s why it’s called Preserve, because we’re preserving all the arteries, all the nerves, all your ducts, and we’re preserving your ligaments so that the implant’s actually inside the ligament.”

“Well, because we’re not cutting anything, everything you were born with will be the same. There’s a higher likelihood that you’ll be able to breastfeed and not have any issues with it. And sensation as well.”

“So the recovery is ultra fast. You’re back to work the next day, you can go back to the gym in two weeks.”

What the Video Leaves Out

Same thing a review leaves out:

“What a first-person review usually leaves out is that the writer’s result started with the writer’s anatomy. A thin, athletic patient with good nipple position and a little breast tissue will get the ballerina look with a small implant or fat transfer alone. A patient with more sagging, a wider chest, or a longer sternal notch to nipple distance will need a lift or a different implant to get anywhere close, and the review will not tell you that.”

“One of the advantages in my practice is that we can simulate the results using the Vectra 3D system and the Crisalix system to visualize the results even before the surgery.”

The hair transplant? “A transplant moves hair; it does not make new hair.”

Full surgical version on Agullo Plastic Surgery, with the Motiva Preserve technique. Consult-room version on Southwest Plastic Surgery. Two more celebrity moms: Cardi B and Jennifer Lawrence.

Why Choose Dr. Agullo

Double board-certified by the American Board of Plastic Surgery and the American Board of Surgery, Mayo Clinic plastic surgery fellowship, Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center, and a Castle Connolly Top Doctor for 13 consecutive years. Trained in Motiva Preserve by Motiva in Costa Rica as one of about 30 selected US surgeons.

Ready to Talk?

Get measured. Then decide. (915) 590-7900, text 1-866-814-0038, or book at agulloplasticsurgery.com/appointments. #StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Told to Lose Weight for Years: What Lipedema Is, and What Liposuction Actually Does

Black and white editorial photograph of a woman in a long fitted dress standing in dramatic studio light, her silhouette in profile. Illustrative image, not a patient. Lipedema commentary by Frank Agullo, MD, FACS.

Two words. Lose weight. She has heard them from her mother, her trainer, two doctors and a stranger at the pool.

So she loses it. Face, arms, waist. The legs do not move. Same thighs, same knees, same bruises from a bump she does not remember.

That is lipedema, and it is one of the most under-named conditions I see. Two days ago I wrote about a citrus supplement the Daily Mail asked me about. Today, the surgery.

Spotting It

“Lipedema is usually symmetric, which is different from lymphedema, which usually only happens on one side of the body. Lipedema usually affects the thighs and the legs. It can be associated with tenderness to palpation, easy bruising, and decreased mobility. It does not affect the hands or the feet. It almost always happens in women, and it starts around puberty.”

Symmetric. Tender. Bruises. Hands and feet untouched. If that is you, the diet was never going to work, and here is why:

“Lipedema usually doesn’t respond to diet and exercise. The patient can lose weight and they’ll lose it around the waistline, but the areas affected by lipedema do not respond. The usual patient has dealt with this problem for many years and has always been told to lose weight, but that in essence does not help.”

Not Your Cousin’s Lipo

Cosmetic liposuction sculpts. Lipedema liposuction protects. The whole operation is built around the lymph channels, because damaging them trades one disease for another.

“I usually perform lipedema surgery through liposuction with a power-assisted device, as it has become much of the gold standard. I prefer to keep cannulas under four millimeters. The main objective is to spare the lymphatics, so as not to create lymphedema or worsen the problem. It is performed under general anesthesia, and the strokes are made longitudinally in order to preserve the lymphatic drainage.”

Thin cannula. Strokes along the leg, never across it. Those two choices are the entire difference.

Why Nobody Should Do It All at Once

“Preferably, the lipedema surgery is staged. Outer thighs and hips first, then inner thighs and knees, then the calves, and the arms last, typically four to eight weeks apart. The staging order is a general guideline, but some patients have an area that bothers them more than others, so these areas can be prioritized during the treatment.”

“For an outpatient procedure, we limit the lipoaspirate to five liters per case, and that is one of the reasons why we stage these procedures. Volumes greater than five liters can create big fluid shifts in the body and require a hospital overnight stay, which usually doesn’t outweigh the benefits. Therefore, repeated smaller sessions can be less costly.”

A surgeon who offers to clear all of it in one marathon session is offering you a hospital bed and a fluid problem. Walk out.

The Insurance Answer, Plainly

“It’s important to note that neither Dr. Agullo nor Southwest Plastic Surgery works with insurance. Lipedema surgery is charged just like liposuction, and the fees can be checked on our fees page as of this writing. The cost is by areas treated. Overall, it is a difficult procedure to have covered under insurance. If you wish to have a physician that takes your insurance, we would be more than happy to refer you to a board-certified plastic surgeon. Nonetheless, many times these procedures will not be approved.”

I would rather say that on the first visit than on the fourth.

A Year Later

“Most patients report improved mobility, less pain, and less bruising. The liposuction will remove the diseased fat or reduce the amount of it. The loose or overhanging skin may need an actual surgical procedure, an excision and lift, for a more cosmetic contour.”

“For mild to moderate skin excess, the procedure could be performed at the same time. For more severe presentations and skin laxity, it’s usually staged and can be performed as soon as three months later, but ideally six months later.”

Moving. Less pain. Fewer bruises. The mirror comes after. The full surgical post, with the candidate criteria, the comparison table and the cost section, is on Agullo Plastic Surgery. The compression-and-massage side, the part that starts before surgery and never stops, is on Southwest Plastic Surgery. Skin after big weight changes, which comes up in the same visit, is here.

Why Choose Dr. Agullo

Double board-certified by the American Board of Plastic Surgery and the American Board of Surgery, Mayo Clinic plastic surgery fellowship, Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center, and a Castle Connolly Top Doctor for 13 consecutive years. Body contouring is the center of my practice.

Ready to Talk?

Stop apologizing for your legs. Get them looked at. (915) 590-7900, text 1-866-814-0038, or book at agulloplasticsurgery.com/appointments. #StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

The Bulge That Stays: What I Tell Patients Years After a Tummy Tuck

Black and white photograph of a woman in a fitted black turtleneck and wide-leg trousers standing by a tall window in a dim studio, looking out, one hand resting at her waist, hard side light. Illustrative generated image, not a real person, not a patient photograph and not a result. Commentary by Frank Agullo, MD, FACS.

“Other surgeons say it’s a complicated revision.”

That quote comes off a RealSelf question I received this summer from someone who’d had a diastasis repair and still wasn’t satisfied with the appearance of their belly. I could have pulled that sentence out of a half-dozen other messages I get, too.

For most patients a tummy tuck is a one-and-done kind of deal, but revisions do happen. And the questions people ask me about them fascinate me, because they reveal things that tummy tuck brochures won’t.

Five such questions, then, lightly edited for publication and stripped of any identifying information (three are from this year, one from 2023 and one from 2019), along with my answers, also slightly adapted for the page.

“My diastasis was repaired and I still bulge. Is muscle re-tightening worth it?”

Answered on RealSelf, Jul 2026.

Often when patients have pregnancy or go through gaining and losing weight we stretch not only the separation between the two muscles called diastasis but also stretch the entire abdominal wall fascia (the connective tissue that is attached to and supports the muscles). Core exercises can help strengthen the muscle but will not address the laxity of the fascia. From your pictures it looks like you may still have laxity of the fascia. Sometimes this is hard to appreciate because when you are laying down it appears much better. It also looks like you still have a little bit of extra fat (this layer of tissue sits between the skin and the muscle called subcutaneous fat).

I would consider a revision to address these areas of concern. When I perform tummy tucks for patients that have previously had a repair of the diastasis I will do what I call a triple plication. This involves plicating the fascia from the sternum (breast bone) down to the pubis to bring the two rectus muscles and their fascia back together, and plicating the oblique muscles and fascia to the lateral edge of the rectus muscles. This essentially creates an “internal corset” or “waist trainer.”

“A revision tummy tuck five years later: what is my risk of necrosis?”

Answered on RealSelf, Jun 2026.

The biggest risk to flaps is not reopening a tummy tuck. The biggest risks are nicotine (even small amounts from a patch, gum or vape), uncontrolled diabetes, aggressive undermining of the flap, aggressive liposuction of the flap, and closing too tightly. Delay actually helps the blood supply!

If a patient is healthy, nonsmoker etc. The risks go way down. I would avoid nicotine for several weeks before hand, eat a protein rich diet as recommended by your doctor, avoid gaining weight between now and your procedure. I would discuss with your doctor making sure the entire flap is not aggressively undermined or liposuctioned at the same time.

“Eight months out, my belly button started draining a little smelly fluid. What should I do?”

Answered on RealSelf, May 2026.

Delayed drainage from the belly button after an abdominoplasty can be from a number of causes. In my experience most commonly this represents a stitch abscess from an infected permanent suture that was placed during the plication of the muscles. Other times there can be a cyst or sinus that forms around a permanent suture that was placed in the deeper layers. Less commonly there can be a more chronic infection in the deeper layers around the area where the muscles were repaired.

Management is dependent on the cause of the drainage but antibiotics alone are unlikely to resolve the problem. Most of the time identifying the cause and removing the permanent suture or draining or excising a sinus or cyst will resolve the problem. See the surgeon who did your procedure for an in person evaluation.

“Almost eight years after my tummy tuck. Do I have dog ears?”

Answered on RealSelf, Dec 2023.

Without preoperative photos and an in-person exam it’s difficult to comment. From your description, it sounds like you have some fullness (combination of skin and fat) at the ends of your tummy tuck scar. Hip dips can accentuate this fullness. Liposuction can help contour the area by removing fat, but fullness from skin cannot be liposuctioned away.

Often in these situations a revision operation lengthening the tummy tuck scar to remove skin is recommended to optimize the waistline contour. Hip dips can also be treated to optimize the hip and waist contour. Fat grafting is sometimes helpful in these situations as well.

“Tummy tuck revision or just lipo?”

Answered on RealSelf, Jan 2019.

Photos don’t show enough information to determine if you have mainly fat that you can pinch in your lower tummy (liposuction could be enough), or if your tummy is firm and there isn’t much you can pinch (plication may be indicated). I would revise the entire length of the scar as well as the dog ear on the left and the fold on the right to make it thinner and better looking.

Your previous surgeon did well keeping the scar as low as possible so that it could be covered by your undergarments. This can make it look like the belly button is a little high. The belly button position can’t be changed up or down much more than a centimeter in a tummy tuck as it’s still connected to the abdominal wall.

What I Would Tell a Colleague

Don’t forget that the midline rectus diastasis repair is not the whole abdominal wall. That fascia that you see stretched out lateral to the rectus muscles? Plicate it (oblique plication) and your patient will notice the difference in their contour.

Don’t be afraid to go back and revise a flap. Five years down the road, your flap’s blood supply will be coming from the sides and be well established. Your flap won’t necrose from reoperation, it will necrose if you do too much lipo on top of that, if your patient smokes, if you put too much tension on closure, etc.

Bulges happen. Make sure you know where that bulge is: have your patient stand up, crunch, pinch that bulge, do an ultrasound to make sure there’s no fluid collection. Then you’ll know if it’s amenable to lipo, needs a plication, needs an extended incision, or just needs a suture taken out.

The full set, including the 15-month bulge after a mini tuck and the c-section shelf, is in the surgical version of this roundup on Agullo Plastic Surgery, and the procedure itself is on the tummy tuck page. Earlier posts cover what lipo and a tummy tuck cost, panniculectomy versus tummy tuck and my three rules for recovery at home.

Why Choose Dr. Agullo

I am certified by the American Board of Plastic Surgery and the American Board of Surgery, did my plastic surgery fellowship at the Mayo Clinic, and teach as Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. Many of the tummy tucks I do are revisions of surgery done elsewhere, in the US and in Mexico.

Ready to Talk?

Call (915) 590-7900, text 1-866-814-0038, or book at agulloplasticsurgery.com/appointments. More of my answers are on RealSelf. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.