
Can a Nose Change Overnight? The Real Rhinoplasty Timeline, From a Surgeon Who Does Them

Black and white editorial portrait of a young man in profile wearing a small white nasal splint, seated in a softly lit consultation room, the splint and the line of his nose the focal point. Illustrative generated image, not a real person and not a patient. Can a nose change overnight, commentary by Frank Agullo, MD, FACS.

One performance. One screenshot. One very long comment thread.

In early November, K-pop fans spent a weekend arguing over whether a member of SEVENTEEN, The8, had rhinoplasty, because his nose appeared different to them from one stage to the next. Koreaboo carried the debate on November 2. Some fans were sure. Others pointed at the lighting. Nobody asked a surgeon, and nobody has any business diagnosing a stranger from a screenshot, so I will not. I have no idea what he has or has not done, and neither does anyone in that thread.

What I can tell you is what a nose does after surgery, day by day, because I watch it every week. A one-day change is almost never a rhinoplasty. The timeline does not allow it.

Day One to Day Seven: You Cannot See the Nose

This is the part the overnight theory skips. After a rhinoplasty the nose is not visible. It is under a splint.

“Surgery is about two to two and a half hours, general anesthesia, home the same day. Splints go on the outside and the inside, so you will be stuffy for about seven days, and then everything comes off. At that point your breathing should be better.”

“You will have a splint on the outside and on the inside that’s gonna be there for a week, and then after a week we’ll take everything off. You’ll see the new nose, but it’s still gonna be a little bit swollen.”

A performer cannot hide a splint under stage makeup. Whoever had surgery that week was not on stage that week.

Week One to Week Six: It Looks Like a Nose, Not the Nose

The splint comes off and the shape is there. It is also swollen, and swelling reads as width.

“The nose will still be swollen. It takes a couple of weeks to start looking better and better, and by about six weeks we are pretty close to the final shape. The nose itself takes about a whole year to keep refining.”

“Only about twenty percent of my patients get bruising under the eyes, and when it happens it takes about two weeks to fade and covers easily with makeup.”

“Usually most people after ten days are okay with other people seeing them, putting on a little makeup if you have any bruising.”

So a fresh rhinoplasty on a stage looks puffier, not slimmer. If a nose looks narrower than it did last month, swelling is not the explanation either way.

Week Six to Month Twelve: The Slow Part

Most of the change shows early. The refinement takes the rest of the year, and it moves in one direction.

“It starts looking really good at six weeks, but it keeps getting better and better for a whole year. So it is a long process, but most of it is really in the beginning.”

“Judging your nose at two weeks is judging a nose that is not finished.”

“If you wanna look your best for Christmas, at least six weeks before.”

That last line is what I tell patients who have an event coming. The idea of a nose quietly turning into a different nose between two shows a few days apart is not how tissue heals.

What Does Change a Nose in a Day

Plenty of things, and none of them are surgery.

What fans saw What it usually is
A slimmer bridge under stage lights Hard side light and contour makeup narrowing the dorsum
A sharper tip on camera Lens distance; a long lens flattens and refines, a phone up close widens
A different profile A three-quarter angle versus straight on, and head tilt
A smaller nose overall Weight loss in the face, which makes every feature read smaller
A nose that “changed” over a few weeks Swelling settling from a procedure done months ago, or nothing at all

There is one treatment that can change a nose in an afternoon, and it is the one I argue with patients about: filler.

“Filler is going to make your nose bigger. All we do with filler is cheat by adding to other places.”

“What we see now is that filler in the nose does not really go away. It spreads. It ends up on the sides, and in the end it makes you look wide.”

So a liquid rhinoplasty can shift a profile overnight. It cannot make a nose smaller, and it tends to make it wider over time. If a nose looks narrower, filler is not the story.

What a Good Rhinoplasty Should Look Like

The honest tell of surgery is not a one-day change. It is a nose that does not fit the face.

“A nose that is too small for the face reads as surgery. A nose that fits reads as a nose.”

“The idea is for the width of your nose to match the corner of your eye.”

“I do an open rhinoplasty, so there is one small incision on the columella, the strip of skin between the nostrils. Everything else is done from the inside. You are going to have a scar, but it is going to be very hard to see.”

When the proportions are right, people stop looking at the nose, which is the whole point, and which is why a careful result gets argued about online for a weekend and then forgotten.

The Timeline, in One Place

Week one, splint on, nose hidden. Week one to six, visible but swollen, bruising in about one patient in five. Six weeks, close to final; exercise can resume. One year, the last refinement, especially at the tip. The surgical side of that first year, what each week looks like and what it costs, is on my practice site. What actually helps swelling settle faster is on Southwest Plastic Surgery. I wrote about a broken nose consult in September and about what a rhinoplasty costs in August.

Why Choose Dr. Agullo

I am certified by the American Board of Plastic Surgery and the American Board of Surgery, completed my plastic surgery fellowship at the Mayo Clinic, and serve as Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. Castle Connolly has listed me as a Top Doctor every year from 2014 through 2026. Rhinoplasty and revision rhinoplasty are a steady part of my practice in El Paso, with 3D imaging at the consult so you see the plan before anyone operates.

Ready to Talk?

Wondering what your own nose would look like, and how long it would take? Come in and look at it in 3D with me. Call (915) 590-7900, text 1-866-814-0038, or request an appointment at agulloplasticsurgery.com/appointments. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.
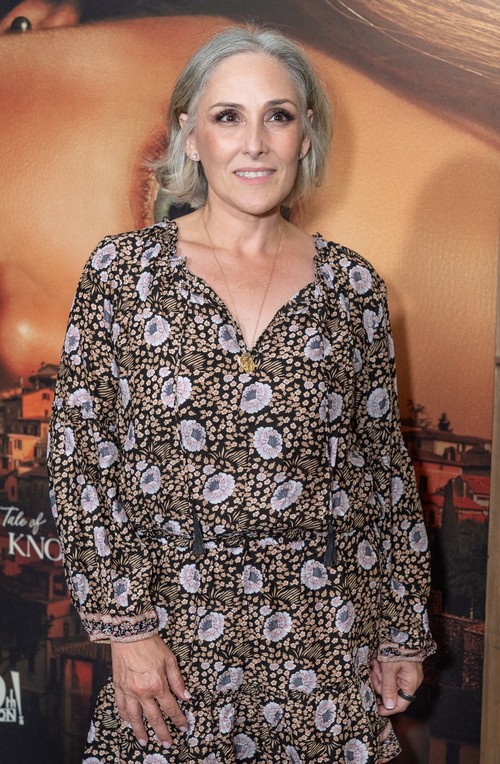
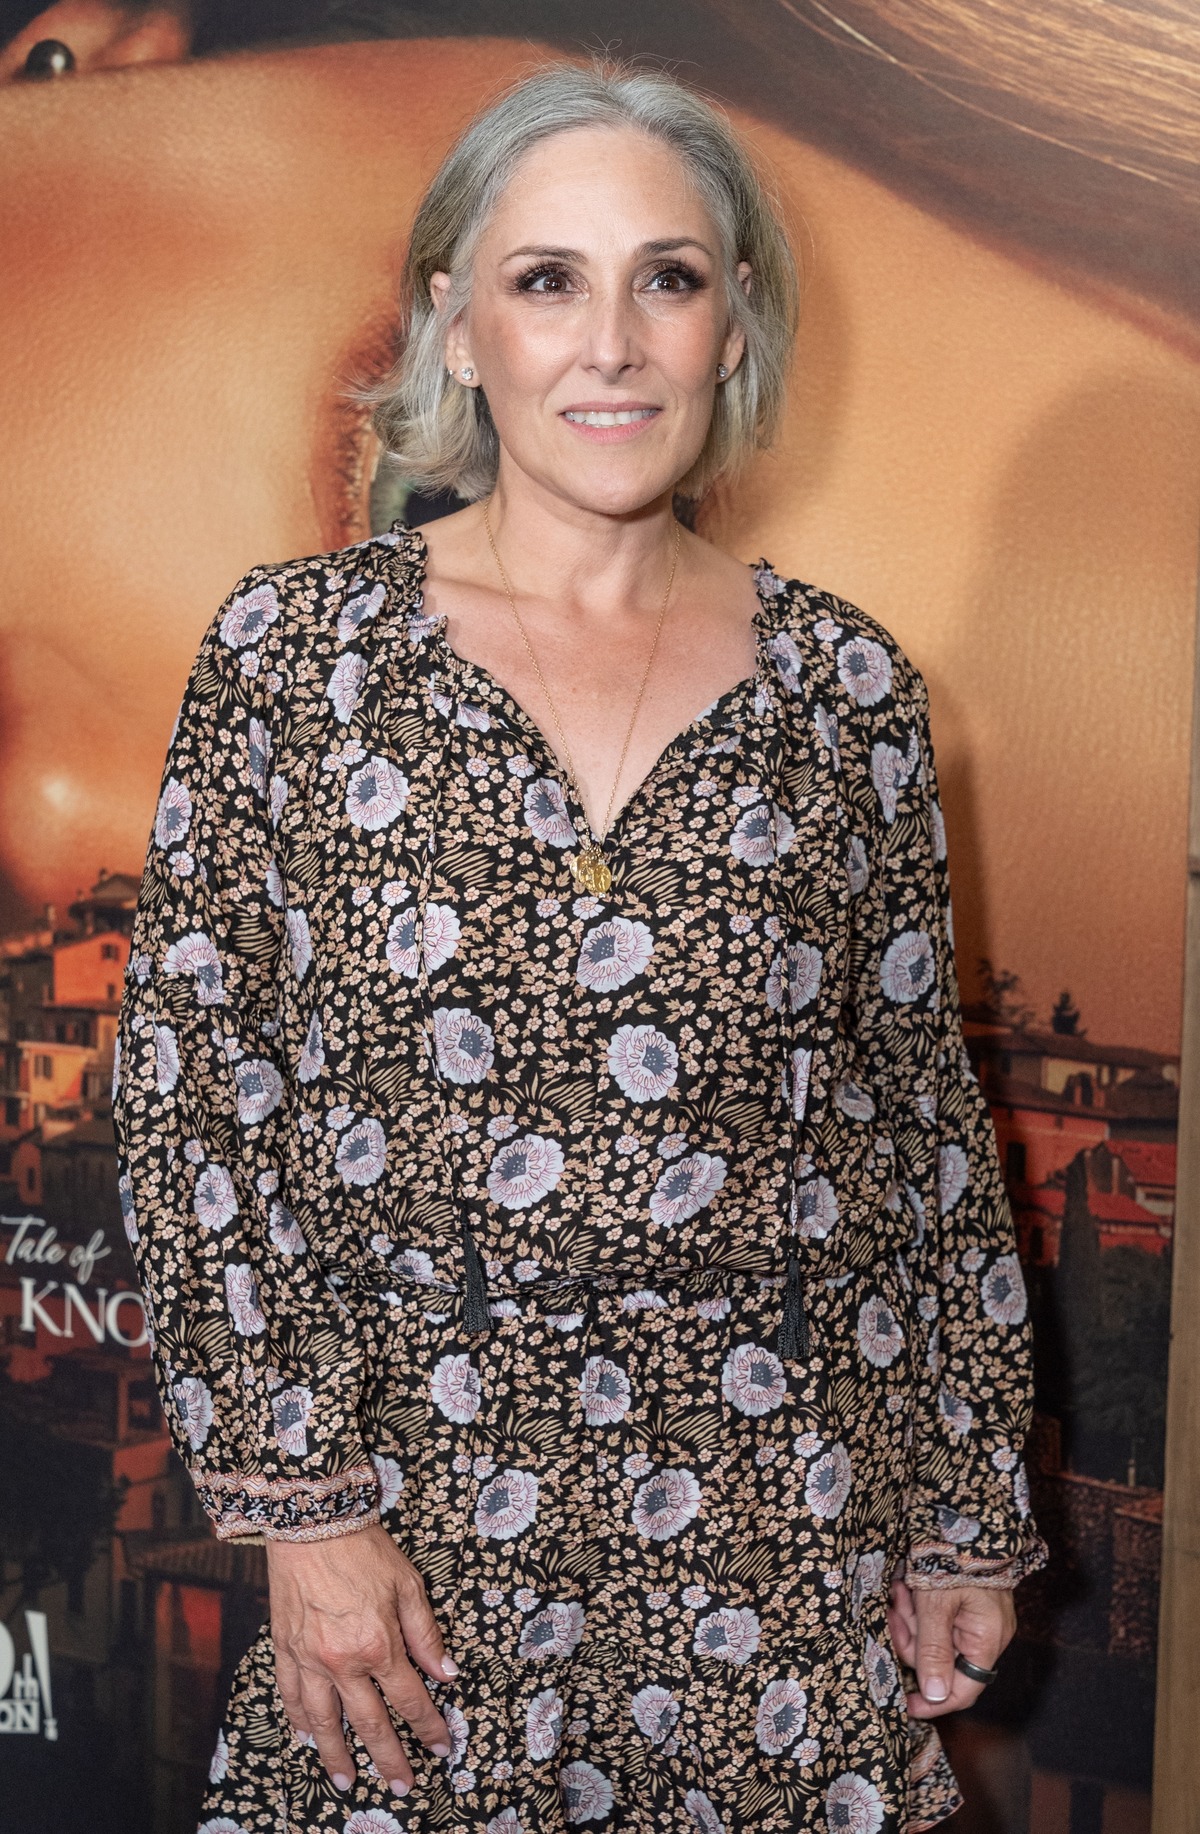
Ricki Lake, Rosie O’Donnell and the Facelift After Weight Loss: What I Check Before Anyone Books

Ricki Lake smiling on the carpet at the Hulu premiere of The Twisted Tale of Amanda Knox in New York, August 19, 2025, after her weight loss and the facelift she has described. Commentary by Frank Agullo, MD, FACS.

Two talk show hosts. Two facelifts. One argument about whether the first one was needed.

Ricki Lake says that when she had her facelift in 2024, Rosie O’Donnell told her it was unnecessary. Then, Lake says, O’Donnell lost about 50 pounds and booked her own. Lake also says she booked hers on impulse, after dropping about 40 pounds, with no research at all. Parade ran the story on October 31; Fox News and AOL picked it up the next day. No surgeon is named, and I am not going to name one or diagnose either woman from a headline.

Ricki Lake smiling on the carpet at the Hulu premiere of The Twisted Tale of Amanda Knox in New York, August 19, 2025, after her weight loss and the facelift she has described. Commentary by Frank Agullo, MD, FACS.
Ricki Lake at the Hulu premiere of The Twisted Tale of Amanda Knox at the New-York Historical Society, New York, August 19, 2025. Photo: lev radin/Shutterstock, editorial use.

I am going to say this, though: I see that exact sequence every week. A patient loses 40 or 50 pounds, usually on a GLP-1, looks in the mirror, and wants a facelift now. Some of them should have one. Some should wait. Here is how I tell the difference, in words I have already put on the record.

Why the Face Goes First

Nobody expects the face to be the first casualty of weight loss. It is.

“The biggest surprise patients see is the change in their face. The face doesn’t have a lot of fat, but the fat it does have is the good fat, the baby fat, what makes you look young.”

“We see the face just melt down because it’s lost all that volume. That’s usually the first thing they notice in the early stages of the weight loss.”

That is not a failure of willpower or of the diet. The skin does not care how the weight came off.

“It’s true, the skin doesn’t know how you did it. Patients lose the weight, the envelope stays, and some patients feel ashamed of it, like they did something wrong. That’s not the fact. It’s just the way things work.”

“Skin stops producing elastin after puberty, so it just doesn’t contract like it does during puberty.”

So when two women in their fifties and sixties drop a combined 90 pounds and both end up on a facelift table, I am not surprised. I have watched the pattern reshape my own practice.

“What I’ve seen in my practice is a lot more patients coming in for facial surgeries after massive weight loss with GLP-1 medications like semaglutide and tirzepatide.”

Check One: Is the Weight Done Moving?

This is the question I would ask either of them first, and it is the one an impulsive booking skips.

“Preferably I want the patient to have lost the weight that they had planned and be weight stable after any facelift procedure. The reason being that oftentimes patients after a facelift tend to lose further weight. And of course, if we lose the volume, then we will have some aging. As the face deflates, the skin tends to sag. So we would lose a lot of the benefit of having done the facelift if the patient continues to lose weight.”

How long is long enough? The GLP-1 timeline is shorter than the old bariatric one, and I have been tracking it.

“What I’ve been seeing is about a six to nine month weight loss and then about a three month stabilization until we’re ready for surgery.”

The other direction matters just as much.

“And the main thing is not to bounce back. When you stop taking it, if we have a bounce back, that can pretty much destroy everything we did, and the fat is not going to come back in the right places necessarily.”

Check Two: Is It Skin, Volume, or Both?

A face after major weight loss is usually two problems wearing one coat. There is loose skin, and there is missing fat. A lift addresses the first. It does nothing for the second.

“Fat is the best filler for a deflated face. A deflated face has lost fat. And what we do when we do fat grafting is replace the fat in those spaces. So it’s like with like.”

That is why almost every facelift I do after weight loss includes fat grafting, and why a lift alone can leave a patient tight but still hollow. The amount of excess skin also decides the operation.

“The differentiator is how much excess skin there is. If there’s substantial excess skin, then we do a deep plane open facelift with an incision in front of the ear. If there’s not a lot of excess skin, we can get away with doing everything through the incisions behind the hairline.”

What you see after 40 to 50 pounds What it usually is What addresses it
Jowls, a soft jawline, a loose neck Excess skin and a dropped deep layer Deep plane facelift and neck lift
Hollow temples, flat cheeks, deep under-eye grooves Lost facial fat Fat grafting, often at the same surgery
Crepey, thin, dry skin over everything Skin quality, not position Resurfacing, RF microneedling, retinoids
All of the above The typical GLP-1 face A plan, not a single procedure

Check Three: Were the Expectations Set, or Skipped?

“Realistic expectations. We have to set that from the beginning, otherwise nobody’s going to be happy.”

Booking with no research is how expectations go unset. A good consultation tells you what the lift will and will not do, and what the first six months look like.

“Patients who have lost a lot of weight, we do these surgeries and we’re pulling as tight as we can, but the skin, because it’s lost that elastin, is going to give again. We lose some of the result over the first six months.”

“A facelift is not finished healing at six weeks or even three months. A great many early complaints resolve on their own by month six.”

And when it is done well, on a stable weight, it holds.

“A well-executed deep plane facelift generally holds its lift for somewhere in the range of ten to fifteen years. Many patients never return to the starting point.”

“A healthy lifestyle, stable weight, and sun protection all go a long way in maintaining results.”

Check Four: Who Is Doing It?

The part of Lake’s account that worries me most is not the surgery. It is “no research.”

“I would stay away from anybody that has one or two or three amazing before and afters and that’s it. You want to see a surgeon that’s posting before and afters every day, and they’re all consistent, and they’re all getting good results.”

“I always feel like when things are too good to be true, they usually are. If a price seems far below what everyone else is charging, you have to ask what’s being cut, the surgeon’s experience, the accreditation of the facility, the type of anesthesia, or the follow-up care.”

Was O’Donnell wrong to call the first facelift unnecessary, then get her own? I have no idea, and neither does anyone reading the headlines. What I do know is that losing 50 pounds changes the answer. The surgical side of that decision, deep plane versus a skin-only lift once the weight is stable, is on my practice site. What the skin needs during the weight loss itself, before anyone operates, is on Southwest Plastic Surgery. I wrote about the face after weight loss in September, about what holds and what drifts at 18 months in October, and about the facelift you can’t see in April.

Why Choose Dr. Agullo

I am certified by the American Board of Plastic Surgery and the American Board of Surgery, completed my plastic surgery fellowship at the Mayo Clinic, and serve as Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. Castle Connolly has listed me as a Top Doctor every year from 2014 through 2026. Deep plane and total endoscopic deep plane facelifts are the center of my practice, and I prescribe and follow GLP-1 patients myself, so I see both halves of this story.

Ready to Talk?

Lost the weight and not sure what your face needs next? Come in and let me look before you book anything. Call (915) 590-7900, text 1-866-814-0038, or request an appointment at agulloplasticsurgery.com/appointments. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.
Twenty New Faces: Why Every After Photo I Just Posted Is a Year Old

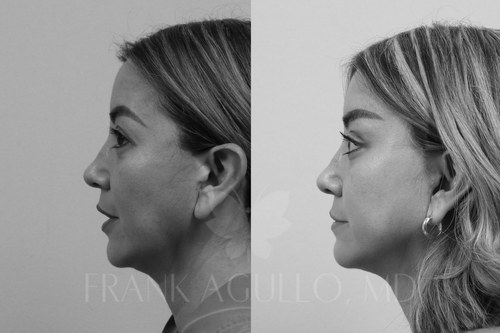
Black and white before-and-after photograph of a facelift patient from the Agullo Plastic Surgery gallery. Actual patient, published with consent.

We added more than 20 new cases. All of the photos are more than one year out for the rhinoplasty and facelifts. We added them for patients to see the latest results using the latest techniques.

A year is the number that matters in that paragraph. A nose at three months is still swollen at the tip; a face at six weeks has healing in it. The photo nobody is in a hurry to take is the result, and it is the only kind I post.

What is in the batch, in the words I gave the office:

I would like everybody to know that there are new before-and-after images for facelift and rhinoplasty in the gallery. The before-and-afters are of open rhinoplasties, primary lower facelifts, neck lifts, and full facelifts. Some of the cases are with the total endoscopic deep plane total facelift, also known as the ponytail lift. Most of the cases are combined with other procedures, including Morpheus8, fat transfer to the face, upper and lower blepharoplasty, buccal fat pad removal, and even a lip lift.

On the noses:

As is usual in my rhinoplasties, they will see very harmonious results that go with the patient’s face. It does not change the patient’s face per se but usually rebalances it and improves the overall aesthetics. They will also notice that all the noses are different and they’re not cookie-cutter templates. Each procedure is individualized accordingly for each patient and their needs. Of course we perform Vectra or Crystalux 3D imaging to help the patient visualize the results before surgery and also to improve communication with me so that we are certain that we’re both on the same page.

They are in the rhinoplasty gallery and the facelift gallery on my surgical site, with a longer note on what each batch shows in the gallery post. More photos are coming over the next few weeks. The practice’s note is on Southwest Plastic Surgery.

I am a double board-certified plastic surgeon, a Mayo Clinic fellowship alum, and a Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. Every photo is my own patient, published with consent. Ask any surgeon you are considering when their after photos were taken.

Call the office at (915) 590-7900, text us at 1-866-814-0038, or book a consultation at agulloplasticsurgery.com/appointments.

#StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Kathy Griffin’s $218,000 Facelift: What a Six-Figure Price Tracks, and What It Does Not

Kathy Griffin smiling on the carpet at the 35th Annual EMA Awards Gala in Studio City, California, October 11, 2025, two months after the facelift she describes. Commentary by Frank Agullo, MD, FACS.

Two hundred and eighteen thousand dollars. Kathy Griffin said the number out loud on a podcast last fall, and E! put it at the top of its celebrity procedures by the numbers roundup this month. Her third facelift, done in August of last year. “It was not cheap,” she said. Then came the part that made me put my coffee down: she called it a bargain, because, by her account, six or seven surgeons in Beverly Hills charge up to a million.

Kathy Griffin smiling on the carpet at the 35th Annual EMA Awards Gala in Studio City, California, October 11, 2025, two months after the facelift she describes. Commentary by Frank Agullo, MD, FACS.
Kathy Griffin at the 35th Annual EMA Awards Gala, Studio City, California, October 11, 2025. Photo: MLM IMAGES Los Angeles/Shutterstock, editorial use.

I’m not her doctor and I have not examined her. I am not going to guess at who her surgeon is, and I am not going to rank her face on some scale. What I can do is read a bill. I write facelift quotes every week, so I have a pretty good idea of what goes into a number like that.

What a Facelift Bill Is Made Of

Let me start with mine, since it is the one I can itemize line by line.

“The fee covers the surgeon’s fee, the anesthesia, the accredited surgical facility, your medical tests, your garments, and your recovery products. Prescription medications from the pharmacy are the one thing you pay separately.”

Then the hours. Mine are not short, on purpose.

“I allow sufficient operating room time to work in a paced fashion, for safety. Low-cost surgeries get compressed to cut anesthesia and operating room fees.”

Then the add-ons, where quotes really diverge.

“With most facelift procedures we also do fat grafting. We usually recommend Morpheus8 with Iriescence PDGF, or the Sciton MicroLaserPeel with Profractional, depending on your skin type. We can also use exosomes or nanofat. We recommend ELIXIR MD, which is LED light therapy, for almost double the speed of recovery. And a lot of patients will require an upper blepharoplasty, a lower blepharoplasty, a lip lift, or an earlobe reduction. Those all do increase the cost.”

Surgeon, hours, anesthesia, facility, city, and whatever else was done under the same anesthetic. The surgeon’s name is the biggest line. The zip code is the second.

What the Price Tracks, and What It Does Not

The number tracks The number does not track
Surgeon demand and experience Whether the result looks natural
Hours in the operating room Whether the midface was actually moved
Anesthesia, facility, nursing How long the result holds
The city (Beverly Hills is its own market) The scar quality
Everything combined in the same anesthetic Whether the patient is recognizable afterward

“Cost varies with the doctor’s experience. Surgeons in high demand consistently deliver good results in a safe environment with top-quality products, and that increases cost.”

Demand sets the price. A price is a signal, not a guarantee, and past a point the signal flattens.

Does $218,000 Buy a Better Face?

No. It buys a surgeon’s time in an expensive city, and probably the full menu in one sitting. The result comes from the plane, the release, and the restraint of the hands.

“I think the deep plane lift and the endoscopic deep plane lift are great procedures, which create very natural and long-lasting results, and we’re seeing patients completely avoid the noninvasive procedures and go straight to the surgical procedures early on.”

“I think patients are becoming a lot more willing to undergo facial procedures, including facelifts, because the results now are actually natural and do not change their overall appearance. So they still have a self identity after these procedures and they’re recognizable; they’re just looking ten to fifteen years younger.”

Recognizable. That is the test, and it is free. More in the facelift you can’t see and month eighteen. No prices in either.

A Third Facelift in 27 Years

Griffin’s first was in 1998, at 38. The third at 64. That is not vanity, that is biology.

“We know that with aging, fat will decrease in the face regardless, so it is a procedure that we probably have to repeat in the future.”

“A facelift will change the position of the tissues,” not the amount of them. The skin keeps aging. Which is why I tell people, “So we have to have realistic expectations, especially when you’re a lot older.” And, from a roundtable in Boston this spring, “if you operate on somebody that’s 30 or 40, it’s not the same as somebody that’s 70 or 80.”

A third lift is also harder: old planes, old scar. Part of what a veteran charges for.

Too Good to Be True Cuts Both Ways

Expensive does not mean safe. Cheap is the one I worry about.

“I always feel like when things are too good to be true, they usually are. If a price seems far below what everyone else is charging, you have to ask what’s being cut, the surgeon’s experience, the accreditation of the facility, the type of anesthesia, or the follow-up care.”

“Our patients get direct nurse access 24 hours a day, and all surgeries are done in an accredited surgical center.”

Ask a six-figure quote the same four questions. What is included, how many hours, who gives the anesthesia, who answers at 2 a.m.

My Numbers, for the Record

My tiers are on the fees page and itemized in what a facelift costs. A full deep plane facelift in El Paso is a fraction of this number. Not less surgery. Less zip code.

Why Choose Dr. Agullo

Dr. Agullo is certified by the American Board of Plastic Surgery and the American Board of Surgery, completed his plastic surgery fellowship at the Mayo Clinic, and serves as Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. He trained in the endoscopic deep plane lift at the Ponytail Academy in Pittsburgh (intermediate) and Santa Monica (advanced). He has been a Castle Connolly Top Doctor for thirteen consecutive years, 2014 through 2026. More than eighty percent of his patients travel to El Paso from across the country.

Ready to Talk?

Bring your quote from anywhere. I will tell you what each line pays for, what I would do differently, and what my number would be.

Call (915) 590-7900, text 1-866-814-0038, or book online at agulloplasticsurgery.com. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Jennifer Lawrence Wants to Be a Sexy Mom: What a Camera Sees, and What Filler Does to It

Kris Jenner on the carpet at the Lucas Museum of Narrative Art opening night in Los Angeles, September 19, 2026. Commentary by Frank Agullo, MD, FACS.

Jennifer Lawrence, 36, two sons, on the cover of The Cut this week. A year after telling The New Yorker she had breast surgery booked, she says she did it (People calls it a lift; other outlets say augmentation; she named no surgeon). She skips filler because it shows on camera. She keeps the Botox light because an actress needs her forehead. A facelift is “someday.” And the line everyone quoted: “I want to be a sexy mom.”

I have not examined her. I will not diagnose her from a magazine cover, and I will not name anyone’s surgeon. But I have every one of those conversations in my exam room, most weeks. Here is my side of them.

What Two Pregnancies Do to a Breast

“It really depends on what happens during pregnancy. If there are big changes in weight, the breasts also get much larger and the skin and tissues get stretched.”

“Once pregnancy and breastfeeding are done, the breast shrinks back in size and the skin somewhat retracts, but not always to the same extent as pre-pregnancy. That is where bottoming out, ptosis or sagginess, and rippling can happen.”

Deflation. The volume leaves, the skin stays. Patients say “nothing bounced back.” Good phrase.

The One Measurement That Decides Lift or Implant

People are going to argue online about what kind of breast surgery she had. A lift? An augmentation? In my office there is no argument about that. We measure.

“The level of droopiness determines whether the patient will require a lift or not. If the nipple areola complex is below the inframammary fold, then a full lift, anchor type incision, will be necessary. If the nipple areola complex is at or slightly above the inframammary fold, I will often recommend a circumareolar lift or donut lift. The ideal sternal notch to nipple areola distance is anywhere from 19 to 22 centimeters. Any number greater than that should consider some type of lift.”

“If the lift is not performed during the augmentation and there is considerable sagging, then the implants will appear to be higher up, even though they are in the right place, and the nipple areola and breast tissue will hang over it.”

Where the nipple sits against the fold. Then what size you want to be. That is the whole decision.

“Once we’ve identified that a lift is necessary, we ask the patient whether they want to stay the same size or slightly smaller, or if they want to be larger. Of course, if they want to be larger, we will need an implant or a fat transfer to the breast.”

What a Lift Looks Like, Honestly

Every lift patient brings wish photos of twenty-five-year-olds with implants and no lift. What I told one of them:

“When we do a lift and use implants, the result ends up being a little more of a natural look. You will have fullness, of course, but we are always going to get a little bit of a slope. That is the limitation of doing a lift, so you are always going to have a little slope even if I go to the biggest implant.”

“A breast lift will always give a perkier look, more upper fullness, and cleavage, but it’s going to have usually a natural slope on top.”

For a mother who wants to look put together at drop-off, not like a reveal, the slope is the point.

What a Camera Sees, and What Filler Does to It

She skips filler because it shows on camera. My version:

“I think we have seen that facial fillers have been quite overdone, and patients are really getting away from looking overfilled and want to look more natural. We have seen that these hyaluronic acid fillers may not dissolve completely, and they do tend to migrate. It seems like they create some kind of inflammatory response in some patients, creating nodules or inflammation. And of course, the feel of a filler is not quite like natural fat, which is squishy and soft, something whose borders you wouldn’t be able to identify the way you can with a filler.”

A lens finds borders. Side light finds a cheek rounder than the bone under it. That is “shows on camera.”

“When patients use fillers, they see that they have to have this redone anywhere from every six months to one year. And what we’re also seeing is that not all of that filler goes away, but it’s migrating and flattening out, so it’s not giving us the volume exactly where we want it.”

“In my practice, I’ve seen more than a twenty to thirty percent decrease in the use of fillers, and a shift toward biostimulators and donor fat grafts instead.”

Long version in my Megan Fox read. Short version: fat is like with like. Filler is a bridge.

Light Botox Is a Technique Choice

She keeps the dose light so the forehead still moves. So do I.

“I myself get botulinum toxin in the forehead, crow’s feet, and glabella lines every three to four months, just to maintain the wrinkle free appearance with a dose that still lets me express my face without looking abnormal.”

“Dose, dilution, injection placement, and product choice matter more than whether you are active or inactive. These are all customized depending on each patient’s consultation. For example, patients with very strong frontalis muscles, glabellar muscles, or masseters will require a higher dose than others.”

Botox does not freeze a forehead. Too much Botox, in the wrong spot, does.

“Unrecognizable” in a Cover Shoot Proves Nothing

Then the cover ran and the comments called her unrecognizable (The Daily Beast covered the pile-on). A cover shoot is lighting, a stylist, a makeup artist, a retoucher and the angle the photographer picked. Surgery moves tissue. A cover moves light.

What I check when I read photos, from a dictation about another actress:

“If you compare the two time frames and look at the brows, they sit in the same position. They have not been lifted. The excess upper eyelid skin remains. The volume of the cheeks is still in the same place, and the jawline is still sharp.”

And the thing that moves a face more than any of us admit, same dictation: “as surgeons we know that 10 or 15 pounds makes a huge difference in the face, whether you gain it or lose it.”

“A facelift will change the position of the tissues, and what we’re seeing on her is a change in the volume or amount of tissue.”

That was about someone else. The method is the same for anyone. Position or volume. Cheek or brow. Structure or light. One cover shot answers none of it.

Kris Jenner, the Friend Who Has Been Through It

Star (via Yahoo) says Kris Jenner has been advising her on surgeons. The article names Jenner’s surgeon. I am not going to. A friend’s referral, even from a friend who had a facelift, gets you a name. The rest is your homework: a consult, a plan, patience.

Kris Jenner on the carpet at the Lucas Museum of Narrative Art opening night in Los Angeles, September 19, 2026. Commentary by Frank Agullo, MD, FACS.
Kris Jenner at the Lucas Museum of Narrative Art opening night, Los Angeles, September 19, 2026. Photo: Kathy Hutchins / Shutterstock.com, editorial use.

I wrote about Kris Jenner at 18 months because month 18 is the honest before-and-after. Month three is the honeymoon. Judge a friend’s result on the 18-month clock, not the premiere photos.

The $30,000 Guess Is a Parlor Game

Page Six (via Yahoo) had surgeons pricing her face from photos at “$30K of procedures.” I do not know what she has had done. Neither do they.

Lighting changes a face. Retouching changes a face. Ten pounds changes a face. Five years changes a face, and she has been in front of cameras her whole adult life. In my office I measure the brow, the cheek, the nipple-to-fold distance. I do not measure a JPEG. Guessing in public with a dollar sign on it is a parlor game, not medicine.

The Facelift “Someday”

She says a facelift is someday. Good answer at 36. The best facelift is the one nobody can see, and there is nothing to lift yet.

Why Choose Dr. Agullo

Double board-certified, by the American Board of Plastic Surgery and the American Board of Surgery. Mayo Clinic plastic surgery fellowship. Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. Castle Connolly Top Doctor for 13 consecutive years. Breast lifts and lift-with-implant cases are among the most common operations in his practice.

Ready to Talk?

Bring the wish photos and I will tell you which of them your breast can become. (915) 590-7900, text 1-866-814-0038, or book at agulloplasticsurgery.com/appointments. #StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

A Deep Plane Facelift at 39, in Istanbul, Then the Flight Home: What the First Two Weeks Are Really For

Black and white photograph of a woman in a long dark coat seen from behind at an airport window at night, a jet blurred beyond the glass, no face. Illustrative image, not a patient. Commentary by Frank Agullo, MD, FACS.
  1. Istanbul. Shopping two days after a deep plane facelift, head still wrapped.

I won’t name names (nor diagnose from afar using a photo taken with a long-lens camera). But two of the questions that occurred to me after seeing that photo, day two after a deep plane facelift procured through a medical tourism agency, are ones I get asked all the time here in El Paso.

The before and after photos as shared publicly on Facebook (The Bhavnish Kakkar, October 26, 2026). Embedded from Facebook; the photos belong to their owners.

The story ran in Fashion Times UK and the Daily Mail last week (I’m sure there were others): 39 y/o Bachelor Australia personality flies to Istanbul for a deep plane facelift and is then photographed out and about (apparently shopping) on day two with her head wrapped. No surgeon named.

  1. If you’re only 39, why on earth would you get a deep plane facelift?

  2. Who’s taking care of you in those first two weeks after a facelift if your surgeon is on another continent?

Thirty-Nine Is Not Too Young. It Is the Whole Point

Why first. Back when I finished my fellowship, a 39-year-old asking for a facelift got tretinoin and a kind smile. Not now. A young patient saw me this fall about her eyelids and we ended up talking about the lift. I told her this, give or take a word.

“As for the lift, the one that’s most natural and lasts the longest would be the ponytail. It’s like a mini, but I don’t like to say mini, because mini is like mini results. It is a deep plane, but with minimal scars.”

“I mention it because, obviously, you’re young, but with this surgery you’re going to look 10, 15 years younger. The good thing is that at this age we can go back to the late twenties, late thirties, and start over. Then ten years after the surgery, we can do it again and go back to the thirties when you’re in your fifties. The sooner we do it, we kind of lock in a younger age. If we do nothing, it ages a little faster. That’s just for you to consider, not something you have to do.”

I want to underline that last line, because it gets lost. At 39 this is an option on the table, not a sentence. Nobody has to.

So why am I having this conversation with people in their thirties at all? “The reason we’re seeing this increase exponentially is that patients are noticing signs of facial aging earlier, or they’ve been on GLP-1s and have had accelerated aging from fat loss in the face and skin sagging.”

And then there is the arithmetic, which is the part people seem to like best. “If you get it at forty, you’re probably going to look like you’re in your early thirties, or even late twenties. But time keeps moving forward, so if we repeat the procedure ten years later, we take you back to that earlier stage of yourself.”

Which Deep Plane, Though

“Deep plane” tells you the layer the surgeon worked in. It does not tell you where the scars are. “The differentiator is how much excess skin there is. If there’s substantial excess skin, then we do a deep plane open facelift with an incision in front of the ear. If there’s not a lot of excess skin, we can get away with doing everything through the incisions behind the hairline.”

A ponytail lift, also called an endoscopic deep plane facelift, leaves its scars inside the hair. It is my go-to conversation with most patients under 45 because there’s typically not a lot of extra skin at that age. Will it look pulled? That’s the question I can set my watch to. A patient asked me exactly that in September.

“I think the deep plane lift and the endoscopic deep plane lift are great procedures, which create very natural and long-lasting results, and we’re seeing patients completely avoid the noninvasive procedures and go straight to the surgical procedures early on.”

What Day Two Looks Like, Anywhere

Shopping in Istanbul on day two after a deep plane facelift? Not shocking to me, honestly. Facelift recovery is physically easy and mentally hard, and I say so before every one of them. “The surgery itself takes about six hours. It’s general anesthesia, and you go home the same day. The good thing about this face surgery is there’s no pain, so the physical recovery is easy. The hard part is you’re going to be swollen, there’ll be some bruising, you’ll look in the mirror and get a little impatient. So it does take about two weeks to start looking good and feel comfortable with other people seeing you. If you have a social event, I’d say six weeks is when you start looking your best. You’ll have a drain that comes out back here. It usually comes out at five days. We remove it, not you.”

Our pre-op nurse says the same thing to every facelift patient before surgery: “So the majority of our patients, around week 3 to 4, they’re regretting what they did. I like to let you know, because once you remember what I tell you when you’re healing, you’re like, okay, she did tell me.”

So the picture of her out with bandages on day two makes sense to me. Day two was never the part I worry about.

The Problem Is Day Five Through Fourteen, and Who Is There

Most of the patients I operate on live out of town, so I have a spiel for this, and here it is. “To be here in El Paso, I recommend staying one week so we can remove the stitches, check that everything is fine, and do the treatments. We have a light treatment called Elixir MD that speeds the recovery almost by double, so that helps you get back to work faster.”

“After seven days here you can go home, and all the follow-ups can be virtual.”

Then there’s the practical stuff. My rule for out-of-town patients is a week near me. I pull the drain myself on day five, take out the sutures, and feel for any fluid under the skin, then you go home and spend two weeks being patient. A medical tourism package has to answer for all of that. Sure, the surgeon may do a beautiful facelift (check that too), but who’s going to remove the drain? Who examines you when there’s a question about swelling on day six? Who reassures you when one side is a little more swollen than the other on day nine and you’re sure the surgery must have gone terribly wrong? And what about the added risk of blood clots and swelling that comes with a long flight in the first week? No help from the booking agent for that, either.

When They Come Home to Us

Every so often one of those patients ends up in my office, which is why I wrote about aftercare for people who had surgery elsewhere last month. The short version of how that goes: “After their surgery, they still need aftercare. Whether it is routine or not, they find themselves in a bind because they cannot easily travel back to see their surgeons.”

“Most surgeons do not accept patients from other surgeons, which makes it difficult for these patients to obtain optimal treatment. We are here for patients, and we are available if we can help.”

What I need from them: “Documentation of the operative report and drain output, as well as any implant cards, is beneficial, but oftentimes not available immediately.”

And what I will not touch early, no matter how much someone wants me to: “In the early stages, we really cannot revise any of the surgery itself.” For the ones who are already unhappy, “patients are usually told to wait until healing has been achieved, which can vary depending on the procedure from three months to a year.”

One more thing, because people flying home tend to forget it. The go-to-the-ER list is the same in every country. “In terms of when to go to the ER, this is very clear, and the patient should already have these instructions from their original surgeon. This includes any changes in vital signs, such as low blood pressure, tachycardia, which is a high pulse rate, fever, lightheadedness, or fainting; redness, purulent discharge, changes in the color of the drain output, specifically if it becomes white, yellowish, or creamy; a fluid collection that keeps growing, shortness of breath or chest pain, swelling in the legs or tenderness in the calves, a breast that suddenly gets larger and painful, or uncontrolled bleeding.”

What I Would Say to Her, or to You

I hope her recovery goes smoothly. Most do, even at 39. The six-week mark will give you a good idea, but a year will show you the final result. I discussed what a settled facelift looks like in my post about Kris Jenner, and the ponytail lift in my facelift you can’t see post.

39 and thinking about it? Ask these questions first, before the price: Which deep plane? Can I hide the scars in my hair? Who takes out the drain, and when? Who do I talk to if, in the third week, I’m freaking out that my reflection looks totally messed up?

The surgical side of this (candidacy at 39, the two deep planes side by side) is on Agullo Plastic Surgery, and the recovery side (LED light, the aftercare package) is on Southwest Plastic Surgery.

I am a double board-certified plastic surgeon, a Mayo Clinic fellowship alum, and a Clinical Associate Professor of plastic surgery at Texas Tech University Health Sciences Center. I trained in the ponytail lift at the Ponytail Academy (the intermediate course in Pittsburgh, the advanced one in Santa Monica), and I do these every week in El Paso.

Call the office at (915) 590-7900, text us at 1-866-814-0038, or book a consultation at drworldwide.com. Find me @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

#StayBeautiful

Kris Jenner at 18 Months: What a Facelift Looks Like When It Has Settled

Black and white photograph of a woman in a long hooded evening cape seen from behind on a stone staircase at night, a line of camera flashes ahead of her, no face. Illustrative image, not a patient. Commentary by Frank Agullo, MD, FACS.

Rome, Saturday night, the All’s Fair premiere. Kris Jenner, 70, in a hooded cape that once belonged to Elizabeth Taylor. Hola says she stole the show and puts the facelift at “last year.” Call it eighteen months.

In April the internet said the lift was slipping. I wrote that one. This is the sequel. No diagnosis, just the clock.

The Honeymoon Is Not the Result

NewBeauty asked me about her in Boston. I told them “two, three months is kind of the honeymoon period for the facelift. That’s when she started posting and announcing that she had the facelift.”

“But on top of that, she had plenty of filters. Those looked amazing. They looked almost unrealistic, which they were.”

“And then when finally a year later we see a picture of her that, you know, they caught without her even being able to pose, you really see the real person.”

Why Month 18 Is the Honest Before-and-After

What my patients hear from us, in order.

“It does take patience because you’ll be swollen. You’ll have bruising. It takes a couple of weeks for people to be comfortable with other people seeing them. So, usually, two weeks, and then if you have any very special events, usually it takes six weeks to really look your best.”

Our pre-op nurse, before every facelift: “For the face procedure recovery, that one is more like a psychological healing. The reason why, because the face is something that we can’t hide. When we do our body, we just put the garment and loose clothes and nobody notices. The face we can’t. So the majority of our patients, around week 3 to 4, they’re regretting what they did. I like to let you know, because once you remember what I tell you when you’re healing, you’re like, okay, she did tell me.”

“You might be one of the lucky ones that don’t swell up a lot, you might be one of the not so lucky that swell up a lot. It varies per patient. Just remember, if you’re very, very swollen, you’re not gonna stay like that.”

“After surgery, firm or hard areas are fibrosis and edema, a normal part of healing. I have patients massage these areas, a lot, and I tell them it keeps getting softer over about three months. It is a lot better at three months than at three weeks.”

Our nurse practitioner, when one side looks different: “You’re always gonna have that one side that’s gonna be a little different than the other depending on the asymmetry of your face. But then again, it’s just so premature right now, because everything’s very swollen, everything’s very irritated. They just removed sutures, so it’s gonna look very red. So we have to let it heal, let the swelling continue to subside.”

Six weeks for an event. Three months for the firmness. A year for the swelling. Eighteen months, nothing left to hide behind.

What Holds and What Drifts

At 18 months Usually holds Usually drifts
Neck and jawline Platysma repair, the cleaned jawline. The deepest work goes last. Neck skin texture, which the lift never treated.
Midface and cheeks The malar fat pad, if it was released and moved as one piece. The midface, if the operation only pulled on the side of the face.
Volume Fat grafts that survived the first six months. Nothing, unless weight changes.
Skin Nothing the lift did. Sun damage, fine lines, pigment.
Scars Faded to a fine line. The earlobe, if closed under tension.

On volume: “Even though we know the patient is going to keep fifty to eighty percent of the volume, that percentage is quite unpredictable, so we are always overfilling.” And: “The good thing is that whatever does stay is going to be quite permanent, and of course maintaining your weight is going to help with that. We know that with aging, fat will decrease in the face regardless, so it is a procedure that we probably have to repeat in the future.”

On weight, from a read I did on another face this fall: “as surgeons we know that 10 or 15 pounds makes a huge difference in the face, whether you gain it or lose it.” And “A facelift will change the position of the tissues,” not the amount of them.

On the midface, the technique question I raised in April is answered at eighteen months, not at eight weeks. More in the facelift you can’t see. A premiere is still a premiere, lighting and glam included; I have not examined her.

A Seventy-Year-Old Face Sets Its Own Terms

“So we have to have realistic expectations, especially when you’re a lot older.”

As I put it in Boston, “if you operate on somebody that’s 30 or 40, it’s not the same as somebody that’s 70 or 80.”

“I think the deep plane lift and the endoscopic deep plane lift are great procedures, which create very natural and long-lasting results, and we’re seeing patients completely avoid the noninvasive procedures and go straight to the surgical procedures early on.”

“I think patients are becoming a lot more willing to undergo facial procedures, including facelifts, because the results now are actually natural and do not change their overall appearance. So they still have a self identity after these procedures and they’re recognizable; they’re just looking ten to fifteen years younger.”

What I Add So the Result Keeps Holding

“In my practice, I’ve really seen a huge increase in face procedures, specifically the deep plane face lift and deep plane neck lift, as well as the total endoscopic deep plane face lift, otherwise known as the ponytail lift. These face lifts are often combined with facial fat grafting, upper and lower eyelid surgery, microneedling with radiofrequency or laser resurfacing, sometimes an upper lip lift, fat transfer to the lips, and earlobe reduction.”

“With most facelift procedures we also do fat grafting. We usually recommend Morpheus8 with Iriescence PDGF, or the Sciton MicroLaserPeel with Profractional, depending on your skin type. We can also use exosomes or nanofat.”

The ten-year version: mother or daughter. Reading a face from photos without diagnosing anyone: Kristen Wiig. The surgical timeline is on agulloplasticsurgery.com; the maintenance version is on the Southwest Plastic Surgery post.

Why Choose Dr. Agullo

Dr. Agullo is certified by the American Board of Plastic Surgery and the American Board of Surgery, completed his plastic surgery fellowship at the Mayo Clinic, and serves as Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. He trained in the endoscopic deep plane lift at the Ponytail Academy in Pittsburgh (intermediate) and Santa Monica (advanced). He has been a Castle Connolly Top Doctor for thirteen consecutive years, 2014 through 2026. His twelve-month photos are the real photos, usually in black and white.

Ready to Talk?

Bring a photo from ten years ago and one that bothers you now. I will tell you what a lift would move, what it would not, and what month eighteen looks like.

Call (915) 590-7900, text 1-866-814-0038, or book online at agulloplasticsurgery.com. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Donor Fat in a Vial: Why I Put Lipoderma Above Filler on My Own Menu

Black and white photograph of a woman in a velvet evening dress seated with her back to the camera at a vanity, the round mirror turned away, a single peony in a glass, no face. Illustrative image, not a patient. Commentary by Frank Agullo, MD, FACS.

I said fat was overtaking the filler era. Now it is on my menu. Lipoderma, donor fat, above HA filler at the MedSpa.

Why fat beats gel

“I think we have seen that facial fillers have been quite overdone, and patients are really getting away from looking overfilled and want to look more natural. We have seen that these hyaluronic acid fillers may not dissolve completely, and they do tend to migrate. It seems like they create some kind of inflammatory response in some patients, creating nodules or inflammation. And of course, the feel of a filler is not quite like natural fat, which is squishy and soft, something whose borders you wouldn’t be able to identify the way you can with a filler.”

“Fat is the best filler for a deflated face. A deflated face has lost fat. And what we do when we do fat grafting is replace the fat in those spaces. So it’s like with like.”

What donor fat is

“We can also use Lipoderma, which is a donor fat graft. This comes already prepared in a vial, so it can be injected in the office in one of the exam rooms, and it gives a lot of the same benefits as using your own graft. These benefits are that the results are soft, very long-lasting, and very natural.”

No harvest. No operating room. Long-lasting, potential to be permanent, no PLLA foreign body response.

What it gives up

“For some patients that don’t want as much downtime, we’ve been using Lipoderma, which is a donor fat graft that gives us very similar results to the patient’s own fat grafting.”

Very similar. Not identical. Your own fat is free by the cc, placed while you sleep. Donor fat is bought by the cc, placed awake. That is the trade.

Who should book it

“The first thing patients notice is the deflation on the face, which we may treat early with fillers like Sculptra, Lipoderma or hyaluronic acid to restore this lost volume.”

The GLP-1 face, early. Before the skin lets go and it becomes a lift.

Menu and prices: the MedSpa post and fees. My ranking of own fat, donor fat and filler: agulloplasticsurgery.com. Last launch: Morpheus8 Cool.

Why Choose Dr. Agullo

I am certified by the American Board of Plastic Surgery and the American Board of Surgery, trained in plastic surgery at the Mayo Clinic, and teach as Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. Castle Connolly has listed me as a Top Doctor for thirteen consecutive years, 2014 through 2026.

Ready to Talk?

Call (915) 590-7900, text 1-866-814-0038, or book online at agulloplasticsurgery.com/appointments. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

Megan to Megatron: How I Tell Filler Migration From a Bad Photo, and Why Frozen Is a Technique Problem

Black and white photograph of a woman seen from behind on a red carpet under a bank of camera flashes, hair in a sleek low knot, no face. Illustrative image, not a patient. Commentary by Frank Agullo, MD, FACS.

A year-old Letterboxd clip, a few side-by-sides, and the internet had a name for it: Megan to Megatron. One of the most shared photos is tagged AI-generated by the account that posted it. No doctor is quoted. IBTimes UK has the timeline.

I do not diagnose a face from a screenshot. Here is what I do instead, with the patient in the chair.

Puffy or Migrated? The Thumb Test

“Normal puffiness or swelling, typical in the mornings or after a late night and heavy salt intake, is soft. We can usually make some of it disappear with cold pressure, and it dissipates during the day.”

“Filler migration requires a history of filler. You have added volume in an area close to where the filler was placed, so it has, in quotations, migrated. It is palpable; filler can be felt outside of where it was originally injected.”

Soft and gone by lunch, salt. Firm, next to where it was put, filler that moved. A photo cannot press on anything.

Why Filler Swells Long After It Was Injected

“Fillers can create a type of inflammation. It may not be constant, but the tissue around the filler itself may swell up.”

“Filler can also block lymphatic drainage and make morning swelling in the injected area even worse.”

“When patients use fillers, they see that they have to have this redone anywhere from every six months to one year. And what we’re also seeing is that not all of that filler goes away, but it’s migrating and flattening out, so it’s not giving us the volume exactly where we want it.”

What Overfilled Actually Looks Like

“I think we have seen that facial fillers have been quite overdone, and patients are really getting away from looking overfilled and want to look more natural. We have seen that these hyaluronic acid fillers may not dissolve completely, and they do tend to migrate. It seems like they create some kind of inflammatory response in some patients, creating nodules or inflammation. And of course, the feel of a filler is not quite like natural fat, which is squishy and soft, something whose borders you wouldn’t be able to identify the way you can with a filler.”

“Really, what I think is that there has been a huge tendency to overfill faces with fillers, and maybe that’s why it’s difficult to count.”

Megan Fox said on a podcast last year that she has had Botox, fillers and laser, and that she does not see the point of shaming people for getting things done. Neither do I.

“Frozen” Is a Technique Problem, Not a Botox Problem

“I myself get botulinum toxin in the forehead, crow’s feet, and glabella lines every three to four months, just to maintain the wrinkle free appearance with a dose that still lets me express my face without looking abnormal.”

“Dose, dilution, injection placement, and product choice matter more than whether you are active or inactive. These are all customized depending on each patient’s consultation. For example, patients with very strong frontalis muscles, glabellar muscles, or masseters will require a higher dose than others.”

“I do ask patients not to exercise for twenty-four hours after a botulinum toxin injection, but this is not because it is going to wear off sooner. It is because I want the solution to stay exactly where I injected it, and strenuous exercise immediately after an injection could increase the risk of the product migrating, complications, and swelling.”

Where My Patients Went Instead

“In my practice, I’ve seen more than a twenty to thirty percent decrease in the use of fillers, and a shift toward biostimulators and donor fat grafts instead.”

“Filler cannot really give us a natural feel. When properly done it can give us a natural look, but it’s often overdone. It can also not give us a long lasting result, and this is where fat has its benefits.”

More: fat grafting overtakes the filler era, under-eye filler does not dissolve, Kristen Wiig photos, a surgeon reads the face, and when the answer is a lift, the facelift you can’t see. The injectables version of this post is on the Southwest Plastic Surgery post; the surgical version is on agulloplasticsurgery.com.

Why Choose Dr. Agullo

Dr. Agullo is certified by the American Board of Plastic Surgery and the American Board of Surgery, completed his plastic surgery fellowship at the Mayo Clinic, and serves as Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. He has been a Castle Connolly Top Doctor for thirteen consecutive years, 2014 through 2026. Facial fat grafting, filler dissolving and revision, and botulinum toxin dosed to keep expression are everyday work in his El Paso practice.

Ready to Talk?

If you are not sure whether what you see is filler, swelling or the light, come in and let me press on it. It takes a minute.

Call (915) 590-7900, text 1-866-814-0038, or book online at agulloplasticsurgery.com. #StayBeautiful

Find me at @RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.

The Facelift Patient Ozempic Sent Me: Thirty-Eight, Sixty Pounds Lighter, and Early

Black and white photograph of a slim woman in a tailored blazer seen from behind in a dark consultation room, a hand mirror face down on the desk in front of her, hard side light, face not visible. Illustrative image, not a patient. Commentary by Frank Agullo, MD, FACS.

Plastic Surgery Practice says the facelift patient is getting younger and the GLP-1 is why. I did not need the article. I needed a bigger schedule.

The Numbers

“About 30 percent of my patients involve a patient who has lost weight on GLP-1s. Before the GLP-1 era, my post-bariatric weight loss surgery practice was about 10 percent.”

“The most common procedure after GLP-1 weight loss right now is a deep plane facelift, a deep neck lift, and/or an endoscopic deep plane facelift, also known as the ponytail lift. This is surprising, because in the post-bariatric patients the most common procedure was a lower body lift, which addressed the abdomen, the buttock and the thighs.”

“The face and neck is the first thing. We’re seeing a lot more since Ozempic started. I’m almost doing three or four every week now. You lose the volume, and of course you’ve already stressed out the skin.”

I wrote up the consult share here.

What I Tell Her First

“Preferably I want the patient to have lost the weight that they had planned and be weight stable after any facelift procedure. The reason being that oftentimes patients after a facelift tend to lose further weight. And of course, if we lose the volume, then we will have some aging. As the face deflates, the skin tends to sag. So we would lose a lot of the benefit of having done the facelift if the patient continues to lose weight.”

Wait. Not forever. Until the scale stops.

What I Tell Her Second

“Fat is the best filler for a deflated face. A deflated face has lost fat. And what we do when we do fat grafting is replace the fat in those spaces. So it’s like with like.”

“Many people are using other fillers like Sculptra. But we have to keep in mind that these fillers create scar tissue and fibrosis, which may make the facelift procedure more difficult. It creates collagen through an inflammatory reaction.”

The filler she got to bridge the wait can make the lift harder. Fat versus filler, the long version.

Which Lift

“The differentiator is how much excess skin there is. If there’s substantial excess skin, then we do a deep plane open facelift with an incision in front of the ear. If there’s not a lot of excess skin, we can get away with doing everything through the incisions behind the hairline. Nevertheless, a full facelift is always going to have the endoscopic portion of the forehead and brows.”

“I think the deep plane lift and the endoscopic deep plane lift are great procedures, which create very natural and long-lasting results, and we’re seeing patients completely avoid the noninvasive procedures and go straight to the surgical procedures early on.”

Early. That is the word the magazine and I agree on. At thirty-eight with good skin and an early jowl, it is usually the ponytail lift, nothing in front of the ear.

What the younger patient says (typical, not a real patient) What I hear
I look tired since I lost the weight Volume. Fat first.
My jawline is gone Early laxity. Ponytail lift once the weight is stable.
My neck is loose Real excess skin. Deep plane with neck lift.
Can filler hold me over Small corrections only. Not the bridge.

Restoration

“More mature patients, and weight loss patients, especially the GLP-1 patients, are looking for a type of restoration. I still feel that the overall majority of patients would like to obtain a better version of themselves, even a better version of themselves before they had their changes through weight loss, aging or pregnancy.”

The surgical version, with the table by skin and weight, is on agulloplasticsurgery.com. The fat-first version is on the Southwest Plastic Surgery post. Earlier: the face after weight loss.

Why Choose Dr. Agullo

Double board-certified, by the American Board of Plastic Surgery and the American Board of Surgery. Mayo Clinic plastic surgery fellowship. Clinical Associate Professor of Plastic Surgery at Texas Tech University Health Sciences Center. Castle Connolly Top Doctor for 13 consecutive years. Ponytail Academy courses in Pittsburgh and Santa Monica.

Ready to Talk?

Lost the weight, lost the face? Come before the filler. (915) 590-7900, text 1-866-814-0038, or book at agulloplasticsurgery.com/appointments. #StayBeautiful

@RealDrWorldWide on Instagram, TikTok, and Snapchat, @Agullo on X, or @AgulloPlasticSurgery on Facebook.
